Accurate diagnosis of prostate cancer relies on systematic clinical evaluation, biomarkers, advanced multiparametric imaging, and targeted tissue sampling. Because early-stage prostate adenocarcinoma often presents as benign lower urinary tract symptoms (LUTS) or remains entirely asymptomatic, diagnostic missteps can lead to either delayed detection of high-risk disease or unnecessary invasive procedures for benign conditions. Recognizing common diagnostic pitfalls is essential for optimizing oncological outcomes and preserving patient quality of life.
1. Clinical Overview and Diagnostic Rationale
What is Prostate Cancer?
Prostate cancer is an invasive malignant neoplasm originating from the glandular epithelial cells of the prostate gland, predominantly localized within the peripheral zone as adenocarcinoma (>95% of cases). Cellular transformation involves multi-step genetic and epigenetic alterations – such as somatic mutations in TP53 or PTEN, TMPRSS2-ERG gene fusions, and BRCA1/2 germline variants – that disrupt normal apoptosis, drive uncontrolled cellular proliferation, and facilitate localized structural invasion or systemic tissue metastasis.
The Critical Role of Early and Accurate Diagnosis
Early-stage prostate cancer is frequently localized and amenable to curative-intent therapies (e.g., radical prostatectomy or definitive radiotherapy) or active surveillance. However, over-reliance on a single abnormal laboratory parameter or misinterpreting non-specific clinical symptoms often leads to diagnostic errors. Differentiating malignant prostatic growth from benign urological pathologies requires an integrated diagnostic continuum rather than isolated testing.
2. Major Diagnostic Pitfalls and Misconceptions in Clinical Evaluation
Navigating the clinical evaluation of prostate cancer involves avoiding several common diagnostic errors.
Pitfall 1: Equating Elevated Serum PSA Exclusively with Prostate Cancer
- The Diagnostic Error: Assuming that an elevated serum Prostate-Specific Antigen (PSA) level (>4.0 ng/mL) is diagnostic of prostate malignancy, prompting immediate invasive biopsy without excluding non-malignant etiologies.
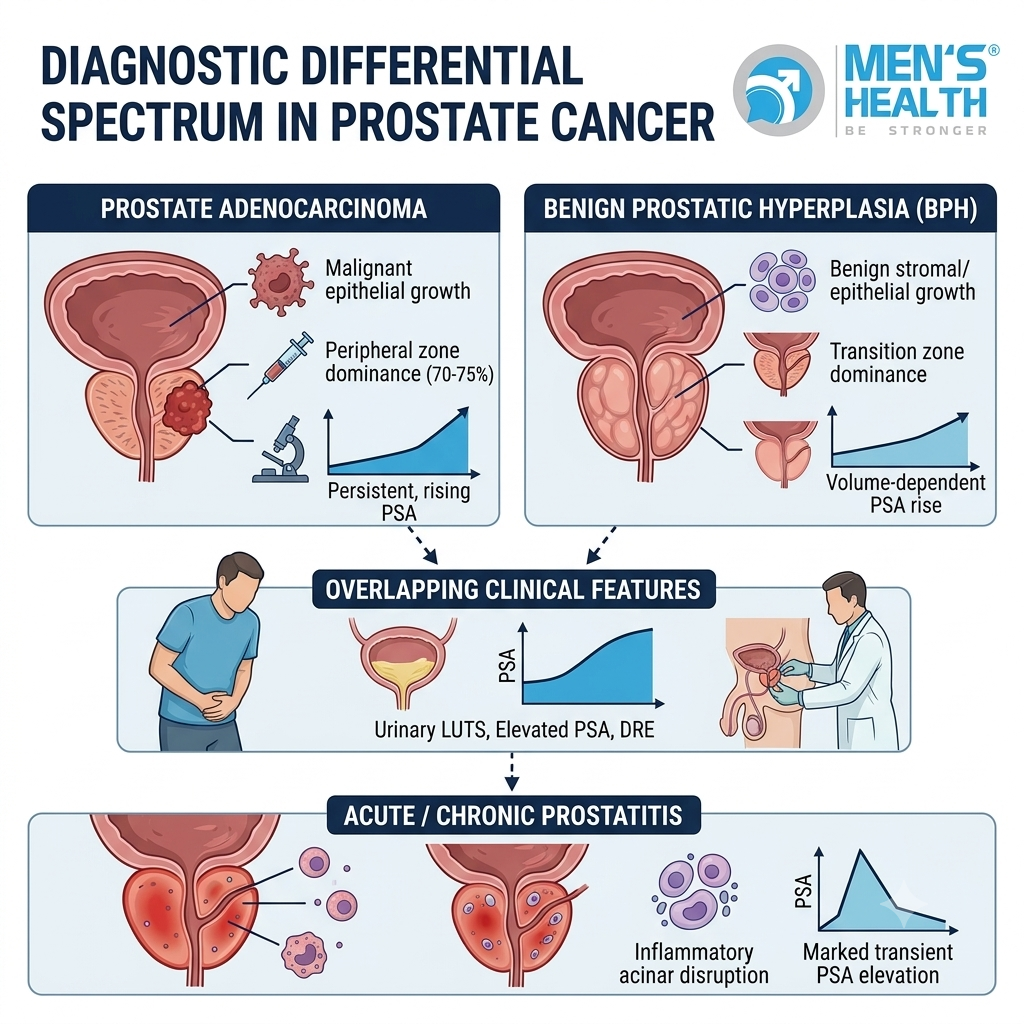
- Clinical Reality: PSA is a tissue-specific serine protease produced by prostatic epithelial cells, not a cancer-specific biomarker. Non-malignant conditions – such as Benign Prostatic Hyperplasia (BPH), acute or chronic bacterial prostatitis, subclinical prostatic inflammation, recent urinary retention, urethral catheterization, or recent ejaculation – can disrupt the basement membrane and release excess PSA into systemic circulation.
- Correction Strategy: Always repeat an elevated serum PSA assay 2 to 4 weeks later under standardized conditions (abstinence from sexual activity and heavy bicycle riding for 48 hours prior to venipuncture) and perform a thorough urinalysis to rule out active urinary tract infections before proceeding to invasive diagnostics.
Pitfall 2: Neglecting Biological PSA Refinements (PSA Density, Velocity, Free-to-Total Ratio)
- The Diagnostic Error: Relying solely on total serum PSA cutoff values while ignoring kinetics, glandular volume adjustment, and molecular isoforms.
- Clinical Reality: A total PSA level of 5.5 ng/mL in a large 90 cm3 prostate gland secondary to BPH represents a normal PSA density (PSAD = 0.06 ng/mL/cm3), whereas the same total PSA in a small 25 cm3 gland yields an elevated PSAD (0.22 ng/mL/cm3), indicating high risk for clinically significant malignancy.
- Correction Strategy: Incorporate secondary biomarker kinetics:
- PSA Density (PSAD): Total PSA divided by total prostate volume (measured via TRUS or mpMRI). A threshold ≥ 0.15 ng/mL/cm3 warrants higher suspicion.
- Free-to-Total PSA Ratio (% Free PSA): Useful in the diagnostic gray zone (Total PSA 4.0 – 10.0 ng/mL). A %Free PSA < 15% suggests malignancy, whereas >25% strongly favors benign hyperplasia.
- PSA Velocity (PSAV): A rapid rise exceeding 0.75 ng/mL/year warrants investigation even if total PSA remains below 4.0 ng/mL.
Pitfall 3: Failing to Adjust PSA Thresholds in Patients Taking 5-α Reductase Inhibitors (5-ARIs)
- The Diagnostic Error: Misinterpreting a “normal” total PSA reading in a patient actively taking finasteride or dutasteride.
- Clinical Reality: 5-ARIs inhibit the conversion of testosterone to dihydrotestosterone (DHT), inducing prostatic epithelial apoptosis and reducing serum total PSA concentrations by approximately 50% after 6 months of continuous therapy.
- Correction Strategy: Multiply the measured serum total PSA level by a factor of 2 (adjusted baseline) for any patient receiving stable 5-ARI therapy for ≥ 6 months. A failure of serum total PSA to decrease by half, or any secondary rise while on 5-ARIs, strongly suggests aggressive prostate adenocarcinoma.
Pitfall 4: Omitting Digital Rectal Examination (DRE) in Diagnostic Workups
- The Diagnostic Error: Skipping digital rectal palpation under the assumption that modern laboratory testing and imaging render physical examination obsolete.
- Clinical Reality: Approximately 10%-15% of clinically significant prostate cancers present with normal serum PSA levels (<4.0 ng/mL) but exhibit palpable abnormalities – such as peripheral zone induration, hard asymmetric nodules, or loss of the central sulcus – on DRE.
- Correction Strategy: Digital rectal examination remains a mandatory clinical assessment alongside serum biomarker testing. Any palpable induration warrants further imaging and tissue sampling, regardless of total PSA levels.
Pitfall 5: Proceeding Directly to Core Needle Biopsy Without Pre-Biopsy Multiparametric MRI (mpMRI)
- The Diagnostic Error: Performing unguided, systematic 12-core transrectal ultrasound (TRUS) biopsies immediately upon detecting an elevated PSA without pre-biopsy pelvic MRI.
- Clinical Reality: Systematic TRUS biopsy alone carries a risk of under-sampling lesions located in the anterior zone or transition zone, while simultaneously detecting low-risk, indolent tumors that may not require aggressive treatment.
- Correction Strategy: Utilize high-resolution multiparametric MRI (mpMRI) before biopsy. Interpreted using the Prostate Imaging Reporting and Data System (PI-RADS v2.1), mpMRI accurately localizes suspicious regions (PI-RADS 4 or 5) and enables targeted MRI-transperineal fusion biopsy, improving the detection of clinically significant disease while reducing unnecessary sampling.
Pitfall 6: Misinterpreting Symptom Profiles (LUTS vs. Malignancy)
- The Diagnostic Error: Assuming that severe lower urinary tract symptoms (hesitancy, weak stream, nocturia) are indicative of advanced prostate cancer, or assuming that an absence of symptoms rules out early malignancy.
- Clinical Reality: Most LUTS result from transition zone expansion in Benign Prostatic Hyperplasia compressing the urethral lumen. Early-stage prostate adenocarcinoma typically originates in the outer peripheral zone away from the urethral lumen and is characteristically asymptomatic. Symptoms like bone pain, gross hematuria, or hematospermia indicate advanced or metastatic disease.
- Correction Strategy: Evaluate LUTS using validated symptom scores (such as the International Prostate Symptom Score – IPSS) while conducting age-appropriate prostate cancer screening independently of voiding complaints.
3. Comparative Clinical and Diagnostic Matrix
| Urological Pathology | Primary Anatomical Zone | Digital Rectal Exam (DRE) | PSA & Biomarker Profile | Diagnostic Modality of Choice |
| Prostate Adenocarcinoma | Peripheral Zone (70-75%) | Hard, asymmetric nodule, loss of sulcus | Persistent rise, PSAD ≥ 0.15, %Free PSA < 15% | mpMRI (PI-RADS 4-5), Targeted Core Biopsy |
| Benign Prostatic Hyperplasia | Transition Zone | Symmetrically enlarged, smooth, elastic | Mild/moderate elevation, PSAD <0.15, %Free PSA > 25% | TRUS volume assessment, mpMRI (PI-RADS 1-2) |
| Acute Bacterial Prostatitis | Diffuse / Global Gland | Exquisitely tender, hot, boggy gland | Marked transient rise (>20-50 ng/mL) | Urinalysis, culture; defer biopsy & repeat PSA post-antibiotics |
| Prostatic Abscess | Focal Parenchyma | Fluctuant, tender focal mass | Variable elevation during acute flare | Pelvic Ultrasound / MRI showing rim-enhancing cavity |
| Prostatic Calculi | Acinar Ducts | Hard, focal nodular sensation | Usually normal unless co-existing BPH | TRUS showing hyper-echoic foci with acoustic shadowing |
4. Evidence-Based Comprehensive Diagnostic Pathway
Establishing an accurate diagnosis requires a structured pathway moving from clinical risk assessment to definitive histopathological confirmation.

- Clinical Risk Profiling & DRE: Assess patient age, family history of prostate or breast/ovarian cancer (BRCA1/2), and perform digital rectal palpation.
- Standardized Serum PSA Evaluation: Measure total PSA, free-to-total PSA ratio, and calculate PSA density using gland volume. Defer testing if acute bacterial prostatitis or severe urinary tract infection is present.
- Pelvic Multiparametric MRI (mpMRI): Combine T2-weighted, Diffusion-Weighted Imaging (DWI), and Dynamic Contrast Enhancement (DCE) sequences. Lesions are classified from PI-RADS 1 (very low risk) to PI-RADS 5 (very high risk).
- Targeted Core Needle Biopsy: Perform transperineal MRI-fusion targeted core needle biopsy for suspicious lesions (PI-RADS ≥ 3). Samples are evaluated using the Gleason Grading System and ISUP Grade Groups (Groups 1 through 5).
5. Medical Pharmacotherapy in Prostate Cancer Management
Pharmacotherapy plays an important role in managing both advanced prostate cancer and co-existing benign conditions.
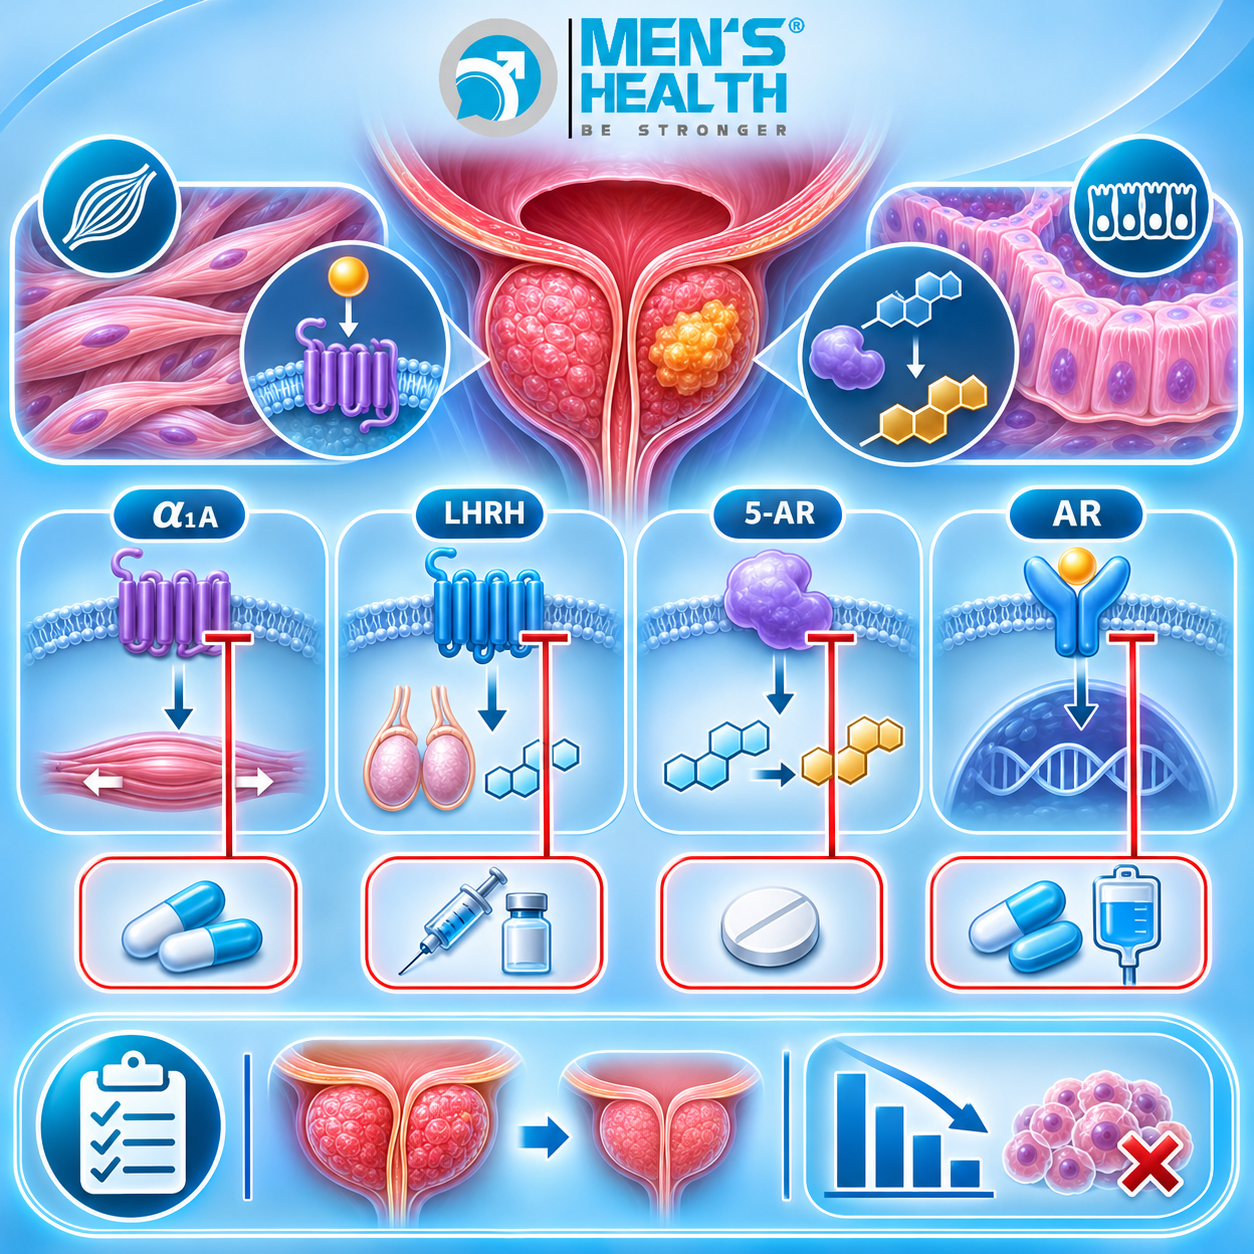
Core Pharmacological Classes
Androgen Deprivation Therapy (ADT – GnRH Agonists & Antagonists)
- Mechanism of Action: Suppresses testicular androgen production. GnRH agonists (e.g., Leuprolide, Goserelin) downregulate pituitary receptors after an initial transient flare, whereas GnRH antagonists (e.g., Degarelix, Relugolix) achieve immediate testosterone suppression.
- Indications: Advanced, metastatic, or high-risk localized prostate cancer combined with radiotherapy.
- Adverse Effects & Precautions: Hot flashes, loss of bone mineral density (osteoporosis), sarcopenia, metabolic changes, and cardiovascular risk.
Novel Androgen Receptor Pathway Inhibitors (ARPIs)
- Mechanism of Action: Competitive inhibition of androgen binding to the androgen receptor, blocking nuclear translocation and DNA transcription.
- Representative Agents: Enzalutamide, Abiraterone acetate, Apalutamide, Darolutamide.
- Indications: Metastatic hormone-sensitive and castration-resistant prostate cancer.
- Precautions: Requires routine monitoring of liver enzymes, blood pressure, lipid profiles, and potential CYP450 drug interactions.
Medications for Co-Existing Benign Conditions (α1-Blockers & 5-ARIs)
- α1-Adrenoceptor Antagonists (e.g., Tamsulosin, Silodosin): Prescribed to relieve dynamic outflow obstruction in BPH by relaxing prostatic smooth muscle.
- 5-α Reductase Inhibitors (5-ARIs – e.g., Finasteride, Dutasteride): Inhibits conversion of testosterone to DHT, shrinking prostatic volume in BPH. Remember to double measured PSA values for accurate cancer screening.
6. Comprehensive Care at Men’s Health Center and Men’s Health Pharmacy
Navigating prostate cancer diagnostics and long-term care requires careful clinical evaluation and multidisciplinary pharmaceutical support.
Men’s Health Pharmacy, an integral unit within the Men’s Health Center ecosystem founded by Dr. Tra Anh Duy (MD, PhD, Spec. II), provides specialized clinical pharmacy services for male urological health. At Men’s Health, patients receive tailored consultations from experienced urologists and clinical pharmacists to ensure that prescribed therapeutic regimens – including ADT agents, ARPIs, α1-blockers, and 5-ARIs – are managed safely, screened for drug interactions, and aligned with individual clinical goals. The facility maintains strict clinical safety standards, individual privacy, absolute confidentiality, and evidence-based practice across all phases of patient care.

7. Lifestyle Modifications and Long-Term Prevention
- Nutritional Optimization: Adopt a Mediterranean-style diet rich in whole grains, legumes, tomatoes (lycopene), and omega-3 fatty acids while limiting processed meats and excessive saturated fats.
- Regular Physical Exercise: Engaging in 150 minutes of moderate aerobic and resistance exercise weekly helps maintain bone density and counters metabolic changes associated with androgen deprivation therapy.
- Weight Management: Maintaining a healthy body mass index (BMI) reduces systemic low-grade inflammation linked to aggressive tumor biology.
- Routine Urological Screening: Men aged 50 and older (or starting at age 40–45 for those with a strong family history or BRCA mutations) should discuss baseline PSA testing and clinical risk evaluation with a urologist.
8. Clinical Diagnostic Pitfalls to Avoid
- Rushing to Biopsy Based on a Single PSA Result: Failing to repeat an elevated PSA test under standardized conditions or after treating underlying subclinical inflammation.
- Forgetting to Adjust PSA for 5-ARI Use: Failing to double total serum PSA values in patients taking finasteride or dutasteride for over 6 months.
- Relying Solely on Total PSA Without Kinetics: Omitting PSA density, velocity, or free-to-total ratios in borderline cases.
- Skipping Digital Rectal Examination: Omitting physical palpation, which can miss PSA-negative malignant nodules.
- Performing Systematic Biopsies Without Pre-Biopsy mpMRI: Sampling blindly without multiparametric MRI mapping risks missing anterior or transition zone tumors.
9. Frequently Asked Questions
Can a man have prostate cancer with a “normal” PSA level below 4.0 ng/mL?
Yes. Approximately 10%-15% of prostate cancers – particularly aggressive or poorly differentiated tumors – occur in men with total PSA levels below 4.0 ng/mL. Performing a Digital Rectal Examination (DRE) alongside PSA testing helps identify these cases.
How does acute prostatitis affect PSA testing results?
Acute bacterial prostatitis causes severe glandular inflammation and acinar breakdown, allowing intracellular PSA to leak into systemic circulation. This can cause transient PSA spikes above 20-50 ng/mL. PSA testing should be repeated 4 to 8 weeks after complete antibiotic resolution.
What is the advantage of mpMRI-guided fusion biopsy over traditional biopsy?
Multiparametric MRI (mpMRI) creates detailed soft-tissue maps graded via PI-RADS. Fusing these MRI images with real-time ultrasound allows urologists to target suspicious lesions directly, increasing the detection of clinically significant cancers while reducing unnecessary sampling.
Why does taking finasteride or dutasteride complicate prostate cancer screening?
These 5-alpha reductase inhibitors shrink prostate volume and lower serum total PSA levels by about 50% after 6 months. Clinicians must double the measured PSA value in these patients to maintain accurate screening thresholds.
Does Benign Prostatic Hyperplasia (BPH) increase the risk of developing prostate cancer?
No. BPH and prostate cancer are separate pathological conditions occurring in different anatomical zones (transition zone vs. peripheral zone). However, both conditions commonly coexist in aging men.
Conclusion and Expert Clinical Advice
Accurately diagnosing prostate cancer requires avoiding common diagnostic pitfalls, such as relying on a single total PSA value, omitting digital rectal examination, or performing unguided biopsies without pre-biopsy multiparametric MRI. Combining clinical examination, PSA kinetics, free-to-total ratios, mpMRI mapping, and targeted biopsy ensures accurate identification of clinically significant cancer while avoiding unnecessary invasive procedures for benign conditions.
Patients experiencing lower urinary tract symptoms, elevated PSA readings, or abnormal physical findings should avoid self-diagnosis or unprescribed medications. Seeking clinical evaluation at a specialized urological facility such as the Men’s Health Center guarantees comprehensive diagnostic accuracy, expert physician management, and dedicated clinical pharmacy support for long-term urological health.