Urinary incontinence in men is a significant lower urinary tract symptom (LUTS) characterized by the involuntary leakage of urine. It severely impacts physical comfort, psychological well-being, and overall quality of life, requiring precise clinical evaluation to identify underlying anatomical or neurogenic causes.
1. Clinical Definition and Underlying Pathophysiology
What is Male Urinary Incontinence?
Urinary incontinence (UI) is defined by the International Continence Society (ICS) as the complaint of any involuntary loss of urine. In men, UI is not an isolated disease entity but a clinical symptom reflecting functional or structural dysfunction of the bladder, the urethral sphincter mechanism, the prostate, or their controlling neural pathways.
Pathophysiological Mechanisms
Micturition relies on a complex balance between urinary storage and voluntary evacuation. During the storage phase, the detrusor muscle must remain relaxed (mediated by sympathetic β3-adrenergic activation and parasympathetic inhibition), while the bladder neck and striated urethral sphincter maintain closure (mediated by sympathetic α1A-adrenoceptors and somatic pudendal nerve input).
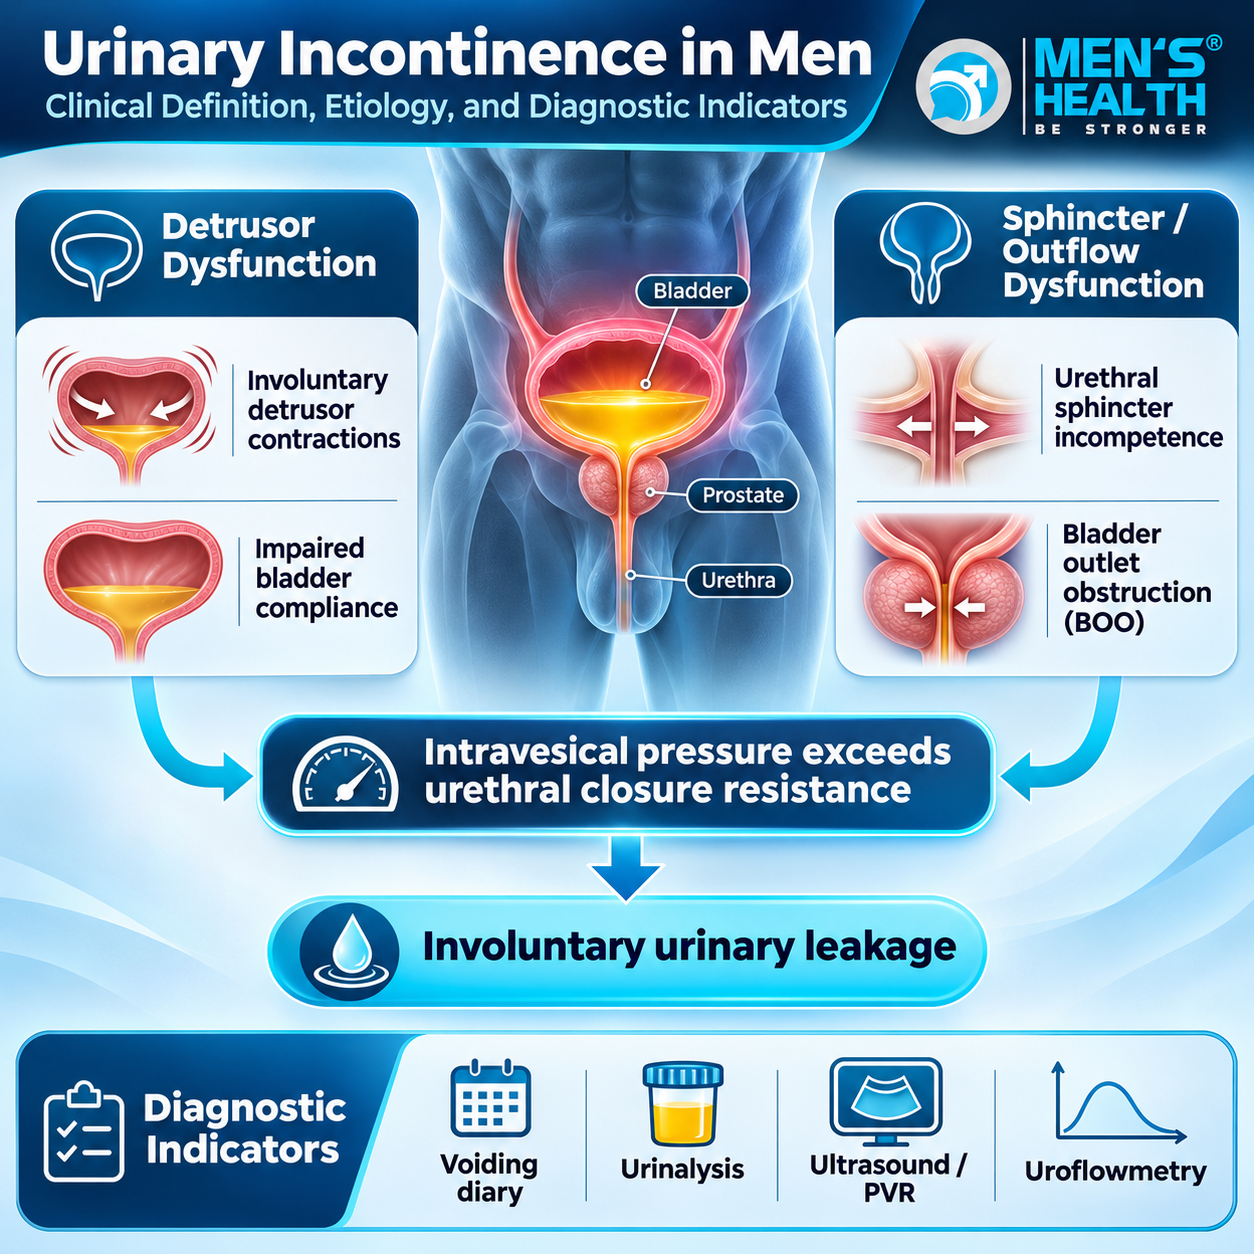
Involuntary leakage occurs through two primary pathophysiological states:
- Intravesical Pressure Exceeding Closure Pressure: Involuntary detrusor muscle contractions generate excessive storage pressure, overriding an intact sphincter.
- Incompetent Urethral Sphincter Mechanism: Structural damage or neurogenic impairment prevents the sphincter from maintaining adequate closure resistance against normal storage pressures.
2. Etiology and Predisposition in Men
Unlike in women, where pelvic floor relaxation is the primary driver, male urinary incontinence frequently stems from prostatic disease, surgical trauma, or central/peripheral neurogenic lesions.
Primary Pathological Causes
- Post-Prostatectomy Sphincter Deficiency: Surgical disruption of the internal bladder neck and trauma to the external striated urethral sphincter during radical prostatectomy for prostate adenocarcinoma or open/endoscopic BPH surgery.
- Bladder Outlet Obstruction (BOO) secondary to BPH: Advanced benign prostatic hyperplasia creates high outflow resistance, causing secondary detrusor hypertrophy, ischemia, reduced compliance, and detrusor overactivity.
- Neurological Disorders: Multiple sclerosis, Parkinson’s disease, cerebrovascular accidents (stroke), spinal cord injuries, and diabetic autonomic neuropathy disrupting central inhibition or peripheral bladder control.
- Chronic Bladder Overdistension (Detrusor Underactivity): Long-standing urinary retention causing chronic stretching of detrusor smooth muscle, leading to impaired contractility and overflow leakage.
Risk Factors
- Advanced age (≥ 65 years).
- History of pelvic radiation, radical pelvic surgery, or lower urinary tract trauma.
- Poorly controlled Type 2 Diabetes Mellitus.
- Chronic metabolic syndrome and abdominal obesity.
- High dietary intake of bladder irritants (caffeine, alcohol, artificial sweeteners).
3. Clinical Types and Diagnostic Indicators
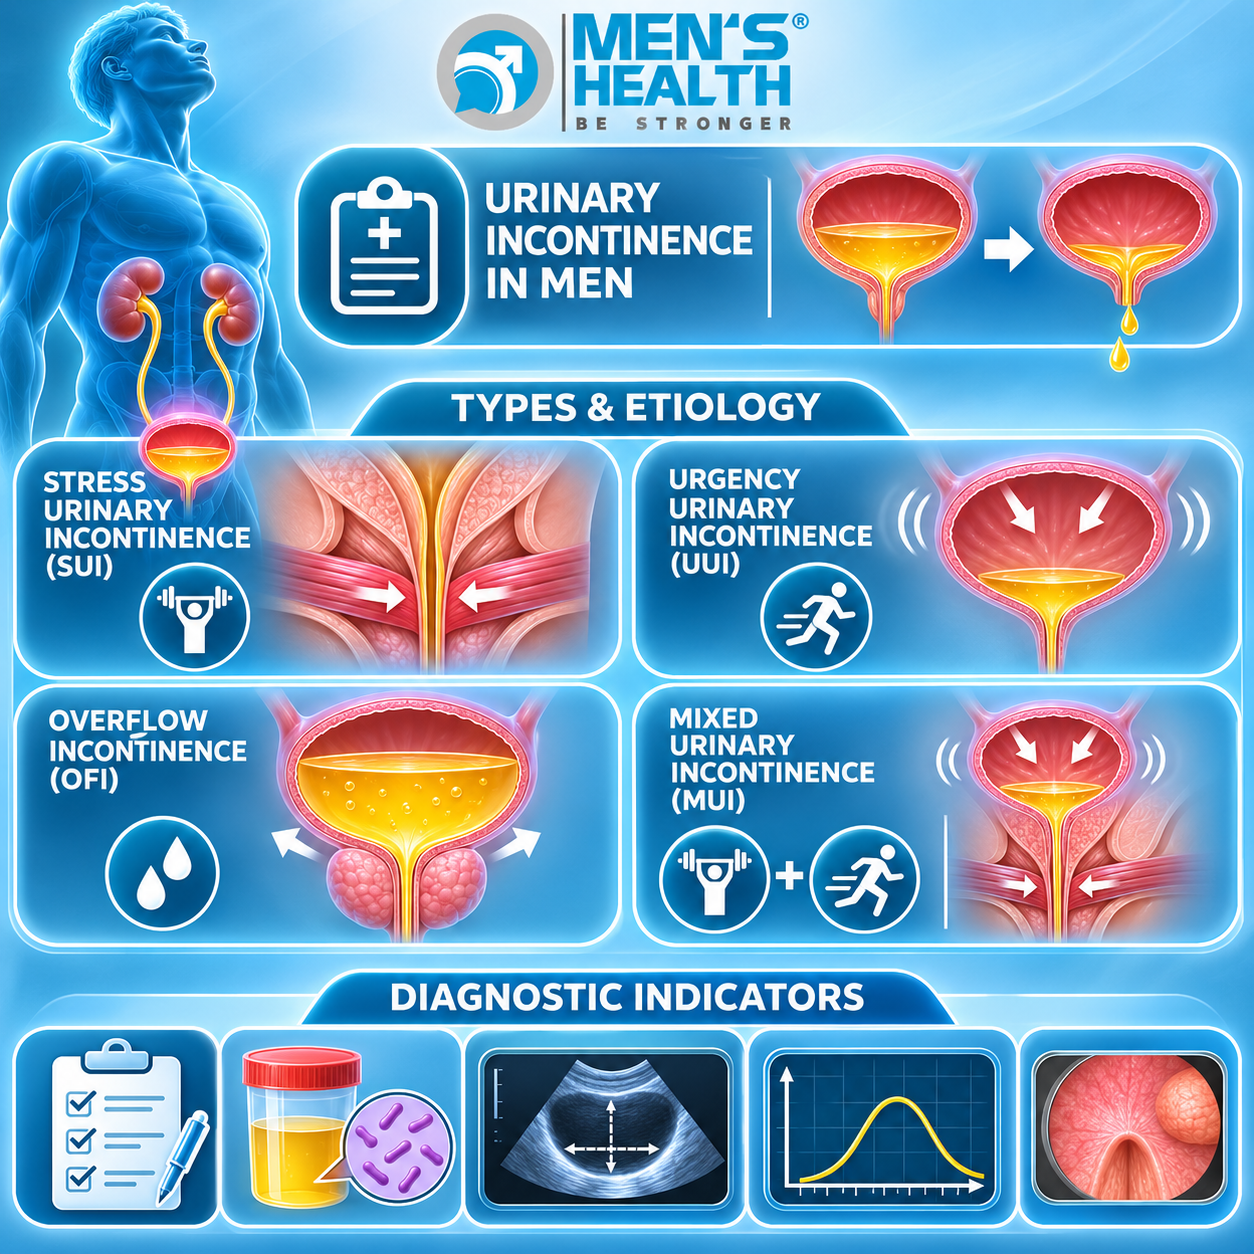
Recognizing the specific clinical presentation allows for precise categorization of male urinary incontinence into four main subtypes.
Symptom Matrix and Features
| Incontinence Subtype | Key Symptom Profile | Pathophysiological Mechanism | Common Etiology in Men |
| Stress (SUI) | Leakage during coughing, sneezing, lifting, or exertion | External urethral sphincter incompetence | Post-radical prostatectomy, pelvic trauma |
| Urgency (UUI) | Involuntary loss preceded by sudden, compelling desire | Involuntary detrusor contractions (DO) | BPH/BOO, neurogenic lesions, cystitis |
| Overflow (OFI) | Continuous dribbling, high frequency, post-void fullness | Intravesical capacity exceeded due to retention | Advanced BPH, strictures, diabetic neuropathy |
| Mixed (MUI) | Features of both exertion leakage and sudden urgency | Combined sphincter weakness and detrusor overactivity | Post-surgical state with pre-existing BOO |
Red Flag Symptoms Requiring Immediate Specialist Workup
- Gross or microscopic hematuria (visible blood in urine).
- Sudden-onset lower extremity weakness, saddle anesthesia, or bowel incontinence (suspected cauda equina syndrome).
- Concurrent fever, chills, flank pain, or systemic toxicity (suspected complicated UTI or pyelonephritis).
- Painful suprapubic mass with an inability to pass urine (acute or high-pressure chronic urinary retention).
4. Comprehensive Diagnostic Protocols
A thorough diagnostic workup moves systematically from basic clinical evaluation to advanced urodynamic profiling.
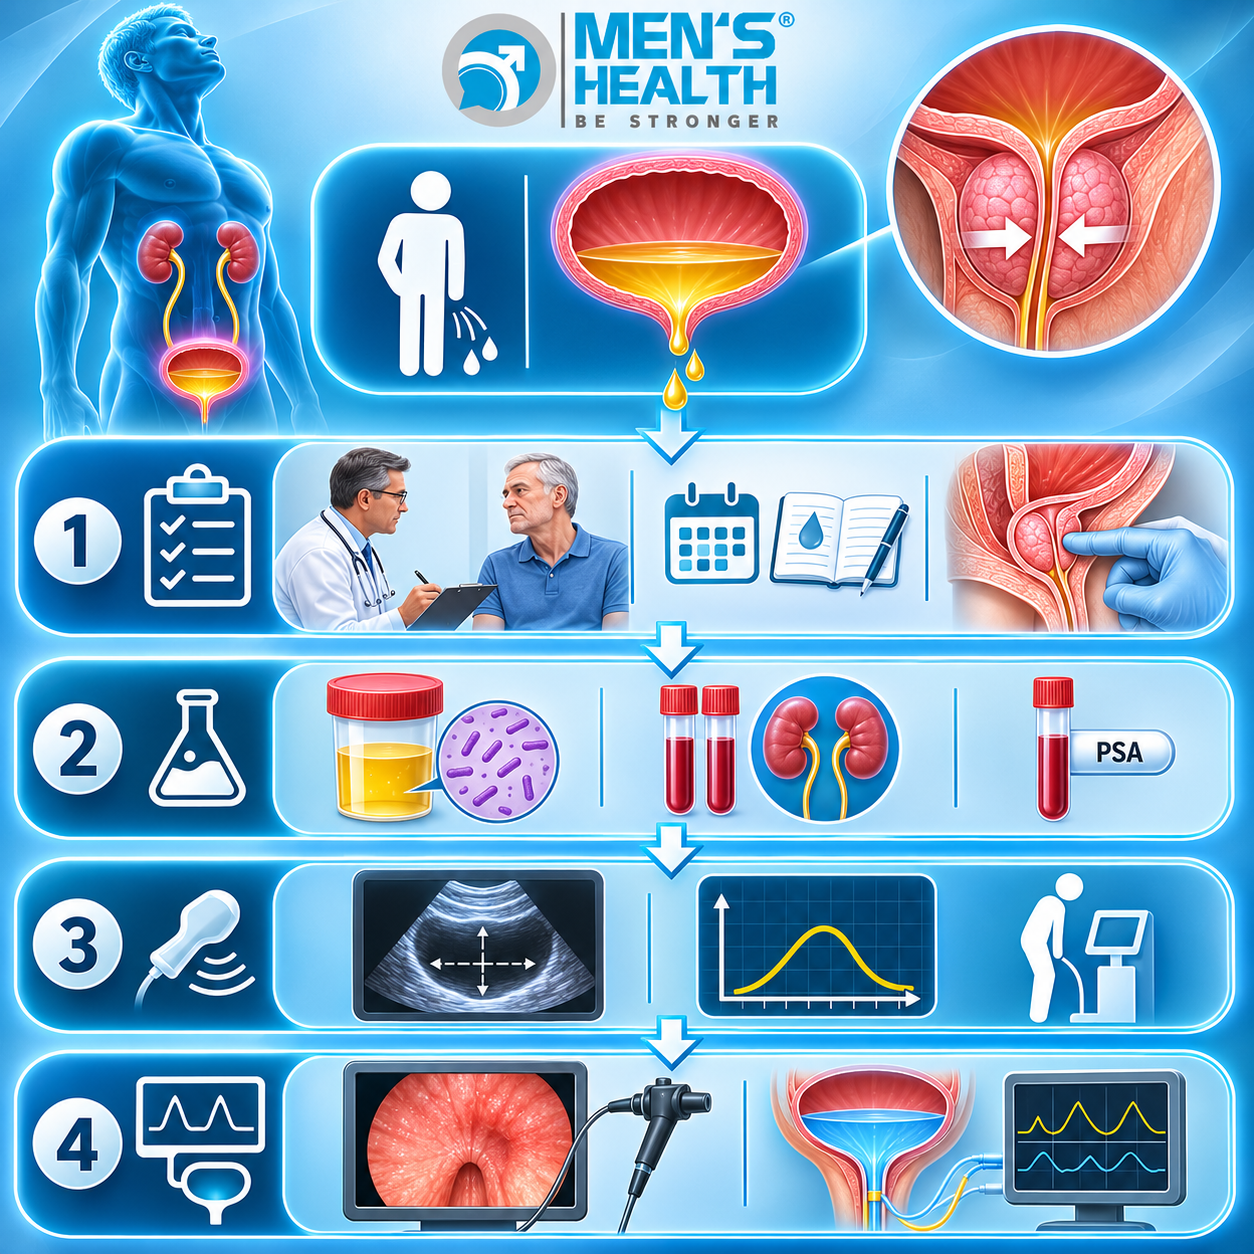
- 3–7 Day Voiding and Incontinence Diary: Documents intake volume, voiding frequency, leakage episodes, pad usage count, and trigger activities.
- Physical and Digital Rectal Examination (DRE): Evaluates prostate size, symmetry, and tenderness while assessing sacral nerve arcs (S2 – S4) via anal sphincter tone and bulbocavernosus reflex.
- Urinalysis and Urine Culture: Standard testing to rule out urinary tract infections, glycosuria, and microscopic hematuria.
- Post-Void Residual (PVR) Ultrasound: Measures residual urinary volume post-micturition. A high PVR (>150-200 mL) identifies underlying retention or overflow mechanics.
- Multi-Channel Urodynamic Studies (UDS): Evaluates filling cystometry, detrusor leak point pressure (DLPP), and pressure-flow dynamics to distinguish detrusor overactivity from sphincter deficiency.
- Flexible Cystoscopy: Directly visualizes the urethral lumen, bladder neck, membranous urethral sphincter, and vesical mucosa to exclude strictures or neoplasms.
5. Comparative Pharmacology and Therapeutic Framework
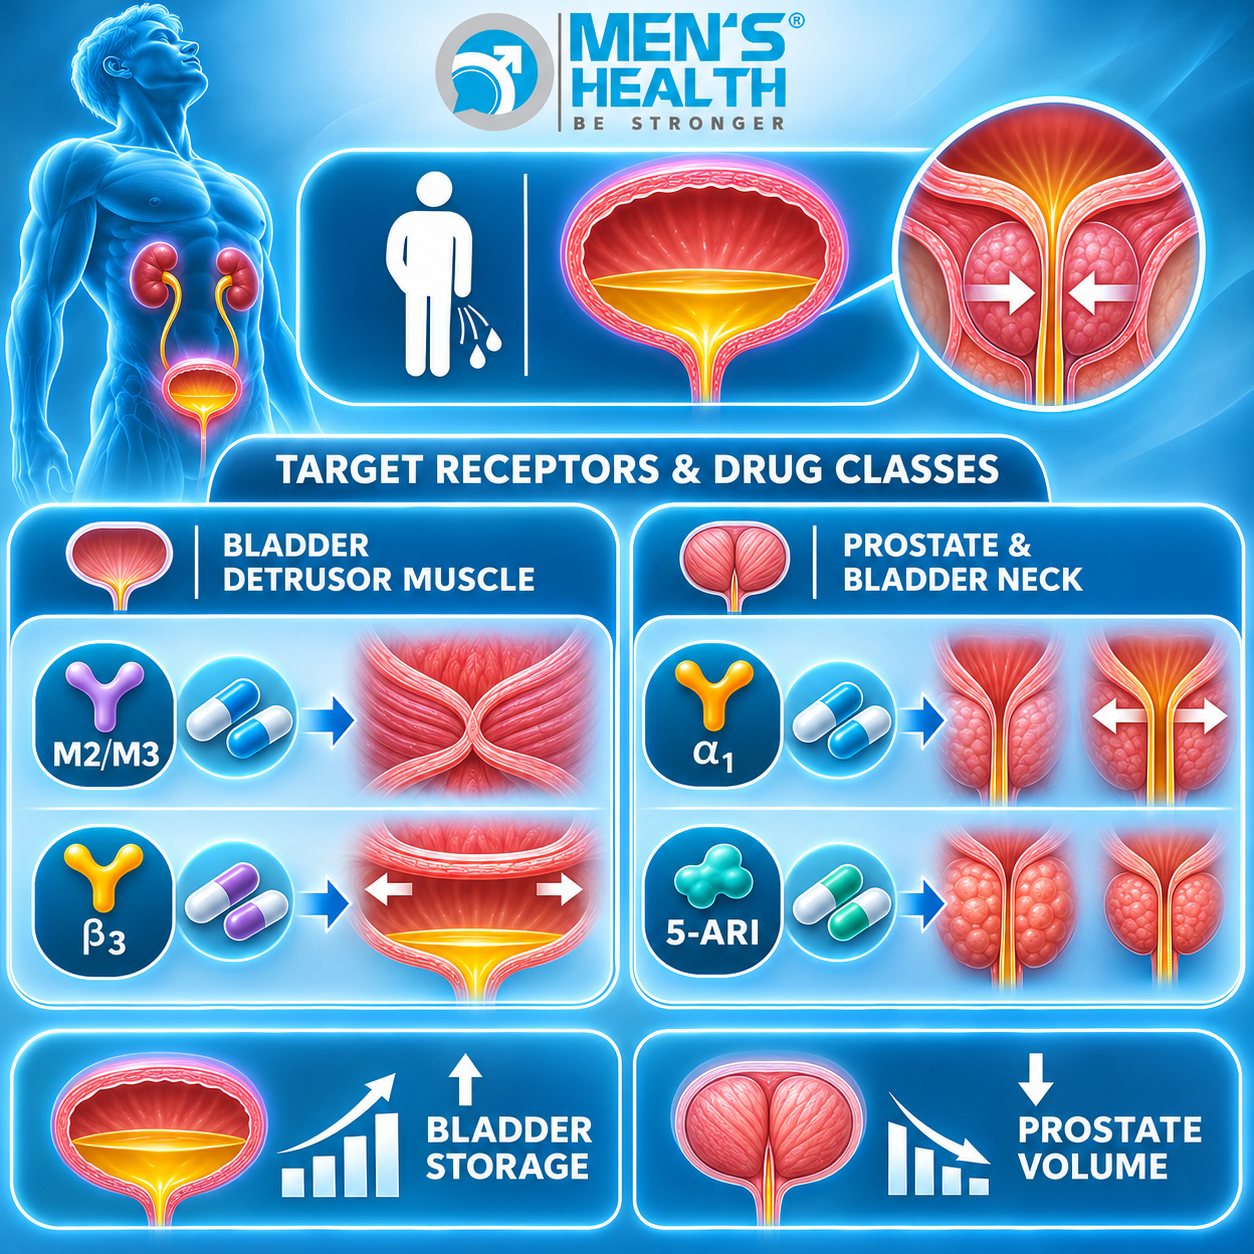
Pharmacotherapy for male urinary incontinence depends on whether the underlying issue is detrusor overactivity, bladder outlet obstruction, or sphincter deficiency.
Main Drug Classes
Antimuscarinic (Anticholinergic) Agents
- Mechanism: Block muscarinic acetylcholine receptors (M2/M3) on detrusor smooth muscle, reducing involuntary contraction frequency and urgency.
- Representative Agents: Solifenacin, Tolterodine, Fesoterodine, Oxybutynin.
- Indication: Urgency Urinary Incontinence (UUI) without elevated PVR.
- Adverse Effects & Precautions: Dry mouth, constipation, blurred vision, cognitive decline. Contraindicated in narrow-angle glaucoma and elevated PVR.
Beta-3 Adrenoceptor Agonists
- Mechanism: Selectively activate β3-adrenergic receptors on detrusor muscle cells, promoting storage relaxation without impairing voiding contractility.
- Representative Agents: Mirabegron, Vibegron.
- Indication: First-line or second-line UUI therapy, particularly in elderly men or those at risk for anticholinergic side effects.
- Adverse Effects & Precautions: Mild hypertension, headache. Contraindicated in severe uncontrolled hypertension.
Alpha-1 Adrenoceptor Antagonists (α1-Blockers)
- Mechanism: Block α1A-adrenoceptors in the prostate stroma and bladder neck, reducing outlet resistance and secondary overflow leakage.
- Representative Agents: Tamsulosin, Silodosin, Alfuzosin.
- Indication: Overflow or urgency incontinence secondary to BPH.
- Adverse Effects: Orthostatic hypotension, dizziness, retrograde ejaculation.
5-Alpha Reductase Inhibitors (5-ARIs)
- Mechanism: Block conversion of testosterone to dihydrotestosterone (DHT), inducing prostatic epithelial apoptosis and reducing gland volume.
- Representative Agents: Finasteride, Dutasteride.
- Indication: Long-term management of BPH-induced overflow or urgency incontinence in prostates >30 mL.
- Adverse Effects: Reduced libido, erectile dysfunction, lowered PSA baseline.
Comparative Drug Class Matrix
| Property | Antimuscarinics (e.g., Solifenacin) | β3-Agonists (e.g., Mirabegron) | α1-Blockers (e.g., Tamsulosin) | 5-ARIs (e.g., Dutasteride) |
| Primary Target | M2/M3 Muscarinic Receptors | β3-Adrenergic Receptors | α1A-Adrenoceptors | 5-α Reductase Enzyme |
| Anatomical Site | Detrusor Muscle | Detrusor Muscle | Prostate & Bladder Neck | Prostatic Epithelium |
| PVR Impact | May Increase PVR | Neutral / Minimal Effect | Reduces PVR | Reduces PVR long-term |
| Cognitive Burden | Yes (CNS Anticholinergic Load) | None | None | None |
| Primary Indication | Urgency Incontinence | Urgency Incontinence | Overflow / BPH-LUTS | BPH prostate enlargement |
6. Procedural and Surgical Options
When conservative and pharmacological therapies fail, targeted surgical interventions offer definitive correction:
- Artificial Urinary Sphincter (AUS): The gold-standard surgical treatment for moderate to severe post-prostatectomy stress urinary incontinence. A fluid-filled cuff is placed around the bulbar urethra and controlled manually via a scrotal pump.
- Male Slings (Transobturator or Retrobulbar): Indicated for mild to moderate post-prostatectomy stress incontinence. A synthetic mesh elevates and compresses the bulbar urethra.
- Sacral Neuromodulation (SNM): Implantation of a neurostimulator targeting the S3 sacral nerve root for refractory urgency urinary incontinence or non-obstructive retention.
7. Professional Care at Men’s Health Pharmacy
Navigating male urinary incontinence requires thorough diagnostic evaluation and coordinated pharmaceutical care.
Men’s Health Pharmacy, a specialized unit within the Men’s Health Center ecosystem founded by Dr. Tra Anh Duy (MD, PhD, Spec. II), provides clinical pharmacy support for male urological health. At Men’s Health, patients receive tailored consultations from experienced urologists and clinical pharmacists to ensure that therapeutic choices—including α1-blockers, antimuscarinics, β3-agonists, or 5-ARIs—align strictly with diagnostic findings and urodynamic profiles. The facility emphasizes professional safety, patient privacy, absolute confidentiality, and evidence-based practice throughout every phase of treatment and long-term follow-up.

8. Lifestyle Interventions and Non-Pharmacological Management
- Fluid Optimization: Maintain balanced daily hydration (1.5 – 2.0 L/day). Avoid fluid restriction (which concentrates urine and irritates the urothelium) and eliminate evening fluid overloading.
- Dietary Adjustments: Reduce or eliminate detrusor irritants, including caffeine, alcohol, carbonated drinks, and spicy foods.
- Pelvic Floor Muscle Training (PFMT): Structured Kegel exercises guided by biofeedback to reinforce external urethral sphincter control during periods of exertion or sudden urgency.
- Timed Voiding: Establishing a fixed voiding schedule every 2 to 3 hours to prevent bladder overdistension and reduce overflow leakage.
9. Common Clinical Pitfalls in Male Incontinence Management
- Empiric Antimuscarinic Prescribing Without PVR Evaluation: Administering anticholinergic drugs to a patient with unrecognized high post-void residual can trigger complete acute urinary retention.
- Misdiagnosing Overflow Incontinence as Pure Urgency: Treating continuous leakage from an overdistended bladder with bladder relaxants worsens urinary retention.
- Ignoring Neurological Red Flags: Treating new-onset incontinence without screening for spinal cord compression or progressive neurodegenerative disease delays critical medical care.
- Unsupervised Self-Medication: Using over-the-counter preparations or unprescribed drugs without formal urological evaluation risks masking underlying prostate malignancy or renal failure.
10. Frequently Asked Questions
What is the most common cause of stress urinary incontinence in men?
The most common cause of male stress urinary incontinence is surgical damage to the internal bladder neck and external urethral sphincter mechanism following radical prostatectomy or endoscopic prostate procedures.
How does benign prostatic hyperplasia (BPH) lead to urinary leakage?
BPH causes chronic bladder outlet obstruction. This leads to secondary detrusor muscle hypertrophy, involuntary detrusor contractions (urgency incontinence), or chronic bladder distension leading to overflow dribbling (overflow incontinence).
Why is measuring post-void residual (PVR) urine volume essential?
PVR measurement via ultrasound determines whether the bladder empties completely. It distinguishes between storage failure (e.g., detrusor overactivity) and emptying failure (e.g., overflow retention), preventing inappropriate drug choices.
How do β3-agonists differ from antimuscarinic drugs for urgency incontinence?
β3-agonists relax the detrusor muscle by activating sympathetic receptors during storage without blocking parasympathetic signals. They carry a significantly lower risk of dry mouth, constipation, and central anticholinergic cognitive side effects.
Can male urinary incontinence be cured completely?
Yes, many forms of male urinary incontinence can be cured or substantially improved through targeted behavioral therapy, precise pharmacotherapy, or surgical interventions such as artificial urinary sphincter implantation or male slings.
Conclusion and Expert Clinical Advice
Male urinary incontinence is a complex, treatable clinical condition with diverse anatomical, neurogenic, and structural etiologies. Achieving optimal outcomes requires accurate diagnosis, including voiding diaries, post-void residual measurement, and urodynamic profiling, to guide therapy safely.
Patients experiencing involuntary leakage, sudden urgency, or continuous dribbling should refrain from self-diagnosis or unprescribed treatment regimens. Seeking clinical evaluation at a specialized facility such as the Men’s Health Center ensures precise diagnostic assessment, specialist physician management, and dedicated clinical pharmacy support for long-term urological health.