Hematospermia (also termed hemospermia) is defined as the macroscopic presence of blood in seminal fluid, ranging in appearance from bright red streaks to a dark brown, rust-colored discoloration. While male genital tract bleeding frequently arises from self-limiting inflammatory or infectious processes, it can be easily confounded with lower urinary tract hematuria or serve as an early clinical marker for structural urogenital malformations, vascular dysplasias, and underlying malignancies.
1. Clinical Overview and Pathophysiologic Mechanisms
Defining Hematospermia and Male Genital Tract Bleeding
Hematospermia involves the breach of vascular integrity anywhere along the multi-glandular pathway responsible for semen production, storage, and transport – encompassing the testicular parenchyma, epididymides, vasa deferentia, seminal vesicles, prostate gland, bulbourethral (Cowper’s) glands, and the prostatic urethra.
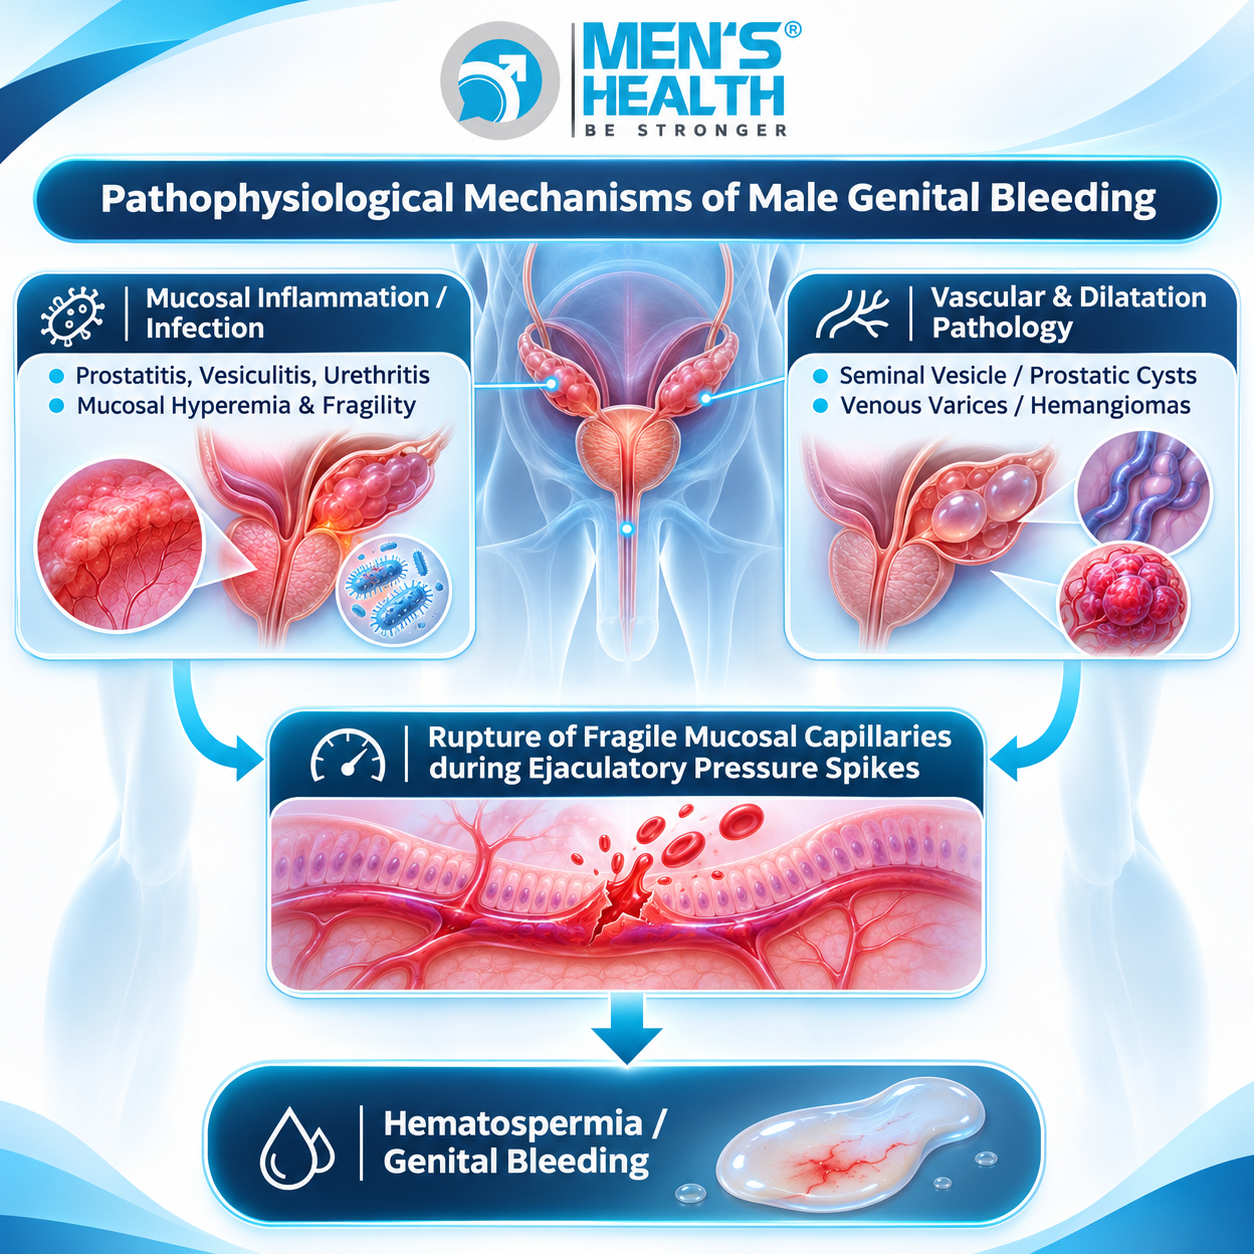
Pathophysiologic Mechanisms
The ejaculatory fluid comprises contributions from the testes/epididymides (), seminal vesicles (), prostate gland (), and bulbourethral glands (). Vascular disruption occurs primarily via three mechanisms:
- Mucosal Hyperemia and Fragility: Acute or chronic inflammation causes tissue edema and hypervascularity. The rapid hydraulic pressure spike during dynamic ejaculatory contraction ruptures fragile subepithelial capillaries.
- Ductal Obstruction and Cystic Stasis: Intraprostatic cysts, ejaculatory duct calcifications, or luminal strictures lead to proximal distension, mucosal stretching, ischemic thinning, and local micro-hemorrhage.
- Neoplastic Neoangiogenesis: Malignant lesions (e.g., prostatic or seminal vesicle adenocarcinoma) express elevated vascular endothelial growth factor (VEGF), forming irregular, thin-walled micro-vessels prone to spontaneous fracture.
2. Etiology and Predisposing Risk Factors
Major Etiological Categories
- Infectious and Inflammatory Diseases (40%−50%): Prostatitis, seminal vesiculitis, epididymitis, urethritis (driven by Escherichia coli, Pseudomonas aeruginosa, Chlamydia trachomatis, Neisseria gonorrhoeae, or Ureaplasma urealyticum), and urogenital tuberculosis.
- Structural and Obstructive Lesions (20%−25%): Müllerian duct cysts, prostatic utricle cysts, seminal vesicle cysts, and ejaculatory duct lithiasis.
- Neoplastic and Premalignant Lesions (5%−10%): Prostate adenocarcinoma, seminal vesicle carcinoma, testicular germ cell tumors, and benign urethral hemangiomas or condylomata.
- Iatrogenic and Traumatic Causes: Transrectal Ultrasound-Guided (TRUS) prostate biopsy (inducing transient hematospermia in up to of cases), prostate brachytherapy, urethral catheterization, or direct pelvic trauma.
- Systemic and Vascular Pathologies: Uncontrolled arterial hypertension, hepatic dysfunction, severe hemophilia, or therapeutic anticoagulation (e.g., warfarin, direct oral anticoagulants [DOACs], antiplatelet agents).
3. Urological Conditions Mistaken for Hematospermia
Differentiating hematospermia from other lower urinary tract and genital bleeding manifestations is critical to avoid diagnostic misclassification and inappropriate therapy.
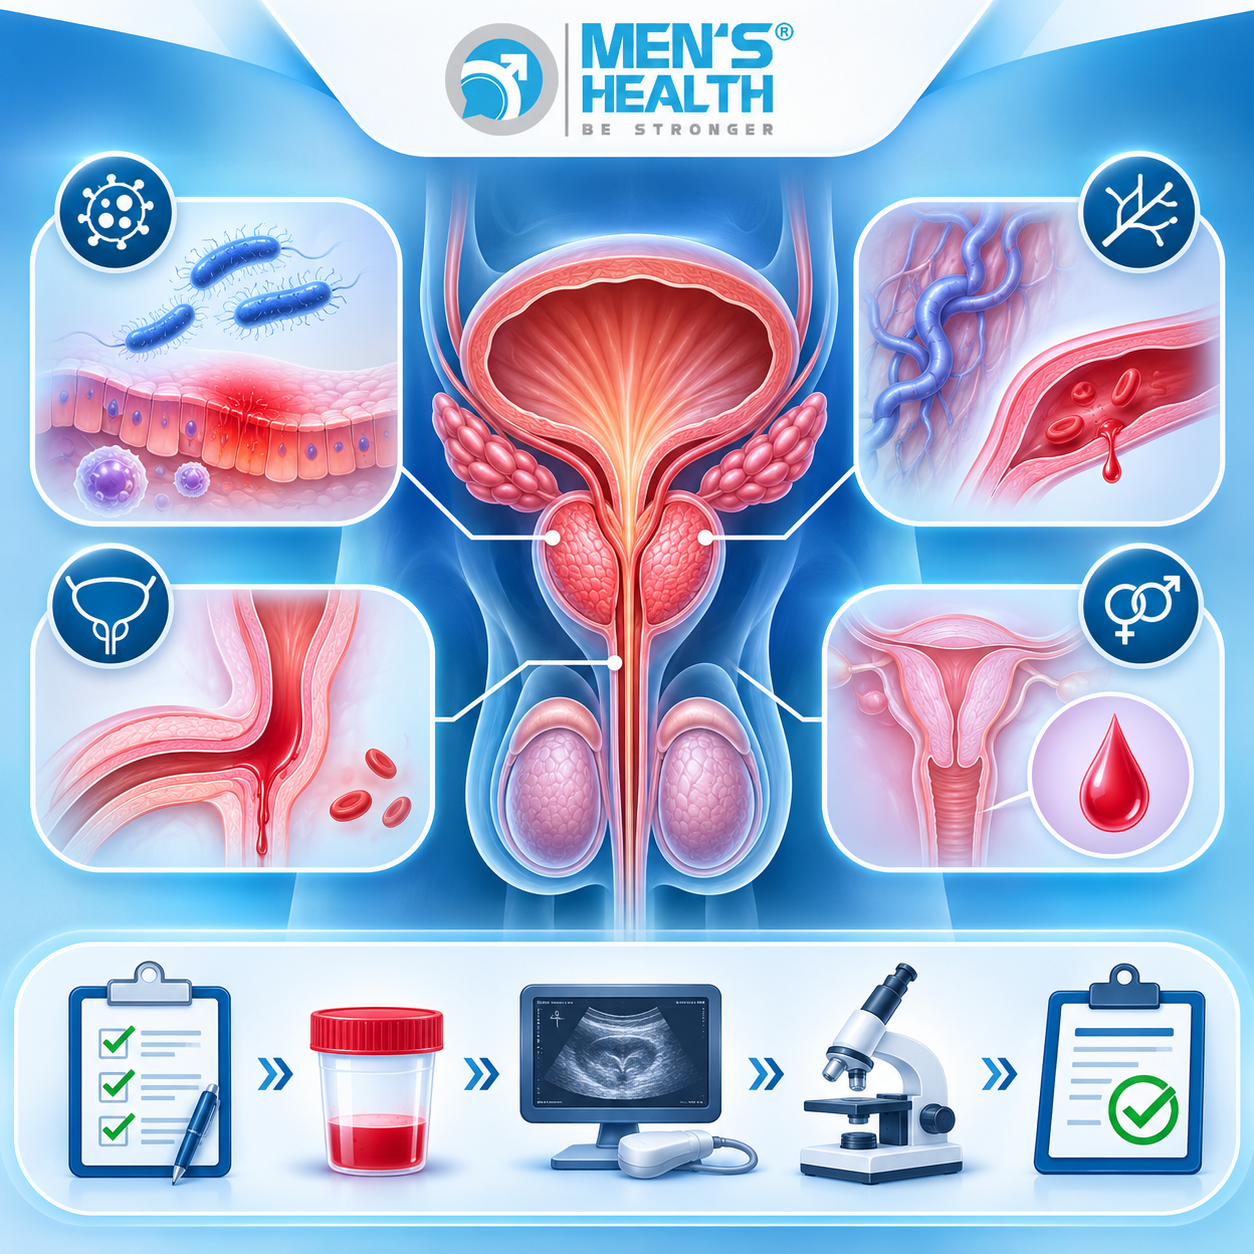
1. Initial/Terminal Hematuria (Bladder and Urethral Pathology)
- Pathophysiological Overlap: Blood originating from the urinary bladder base, trigone, or anterior urethra can remain in the urethral lumen post-micturition and contaminate subsequent ejaculatory fluid.
- Distinction: True hematuria manifests during voiding (initial, total, or terminal stream), whereas hematospermia presents exclusively during or immediately following ejaculation.
2. Urethrorrhagia (Spontaneous Urethral Bleeding)
- Pathophysiological Overlap: Urethrorrhagia refers to spontaneous blood discharge from the urethral meatus independent of both micturition and ejaculation, typically caused by anterior urethral trauma, urethral stricture disease, or meatal hemangiomas.
- Distinction: Urethrorrhagia leaves fresh blood spots on undergarments between voiding episodes, whereas hematospermia requires ejaculatory muscle contraction to expel the blood-admixed semen.
3. Acute Bacterial Prostatitis and Prostatic Abscess
- Pathophysiological Overlap: Severe prostatic inflammation induces extreme tissue hyperemia, causing both dysuria/hematuria and hematospermia.
- Distinction: Bacterial prostatitis presents with systemic febrile illness, perineal pain, pelvic heaviness, and severe dysuria, whereas isolated hematospermia is frequently painless.
4. Bladder Urothelial Carcinoma and Prostatic Adenocarcinoma
- Pathophysiological Overlap: Neoplastic lesions near the bladder neck or prostatic urethra can bleed into both the urinary and genital delivery tracts.
- Distinction: Bladder tumors primarily cause painless gross hematuria (often with clots), whereas prostate cancer presenting with hematospermia typically occurs in older men with elevated serum PSA levels or abnormal digital rectal examinations.
5. Pseudo-Hematospermia
- Pathophysiological Overlap: Macroscopic blood observed on the male genitalia or condom following sexual intercourse that does not originate from the male reproductive tract.
- Distinction: Caused by partner-derived vaginal, cervical, or vulvar bleeding (e.g., menses, cervical erosions, post-coital vaginal lacerations). Confirmation requires examining semen voided into a sterile container via masturbation.
4. Differential Diagnostic Matrix
| Clinical Condition | Primary Bleeding Source | Timing of Blood Appearance | Associated Symptoms | Key Diagnostic Findings |
|---|---|---|---|---|
| True Hematospermia | Seminal vesicles, prostate, vasa | Admixed directly within semen | Ejaculatory discomfort or painless | TRUS/mpMRI shows seminal vesicle/prostate pathology |
| Gross Hematuria | Kidneys, ureters, bladder | Present throughout voided urine | Dysuria, flank pain, or painless | Microscopic pyuria/hematuria; cystoscopy shows mucosal lesions |
| Urethrorrhagia | Anterior or bulbar urethra | Spontaneous discharge between voids | Staining on undergarments, dysuria | Urethroscopy confirms anterior urethral lesion or stricture |
| Prostatic Abscess | Prostatic parenchyma | Present in both urine and semen | High fever, chills, severe perineal pain | DRE shows tender, fluctuant prostate; pelvic US reveals hypoechoic cavity |
| Pseudo-Hematospermia | Female partner genital tract | Stained exteriorly post-coitus | None in the male patient | Normal male urinalysis and sterile semen examination |
5. Comprehensive Clinical Diagnostic Pathways
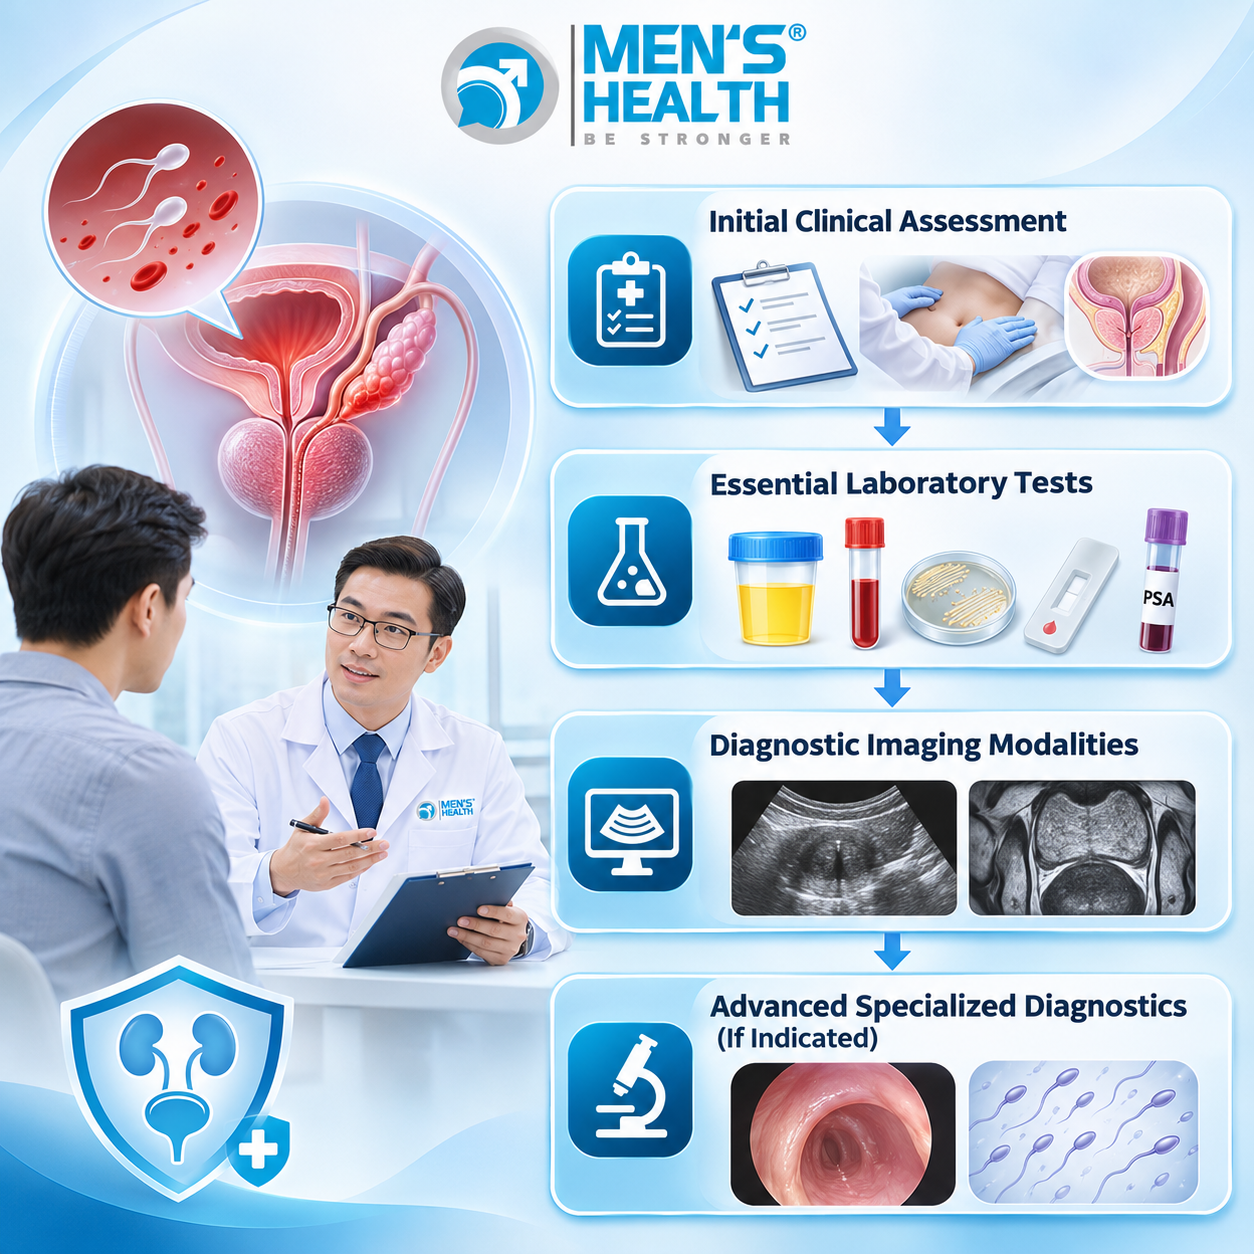
- Detailed Clinical History: Evaluates bleeding duration, fluid color (bright red vs. dark brown), relationship to micturition versus ejaculation, recent urological procedures (e.g., prostate biopsy), and sexual partner status.
- Physical and Digital Rectal Examination (DRE): Evaluates abdominal tenderness, scrotal structures (testes, epididymides, vasa deferentia), and prostate architecture (size, symmetry, tenderness, nodularity).
- Laboratory Profiling: Urinalysis and urine culture exclude UTIs; NAAT screens for C. trachomatis and N. gonorrhoeae; serum PSA screens for prostatic malignancy in men years.
- High-Resolution Pelvic Imaging: Transrectal Ultrasound (TRUS) identifies prostatic cysts and calcifications. Multiparametric Pelvic MRI (mpMRI) serves as the definitive modality for high-resolution evaluation of seminal vesicle hemorrhage and localized prostate cancer (PIRADS categorization).
- Flexible Cystourethroscopy: Indicated in patients with persistent hematospermia (weeks), concurrent gross hematuria, or suspected urethral vascular lesions.
6. Pharmacological Management Strategies
Medical management depends strictly on the established underlying etiology.
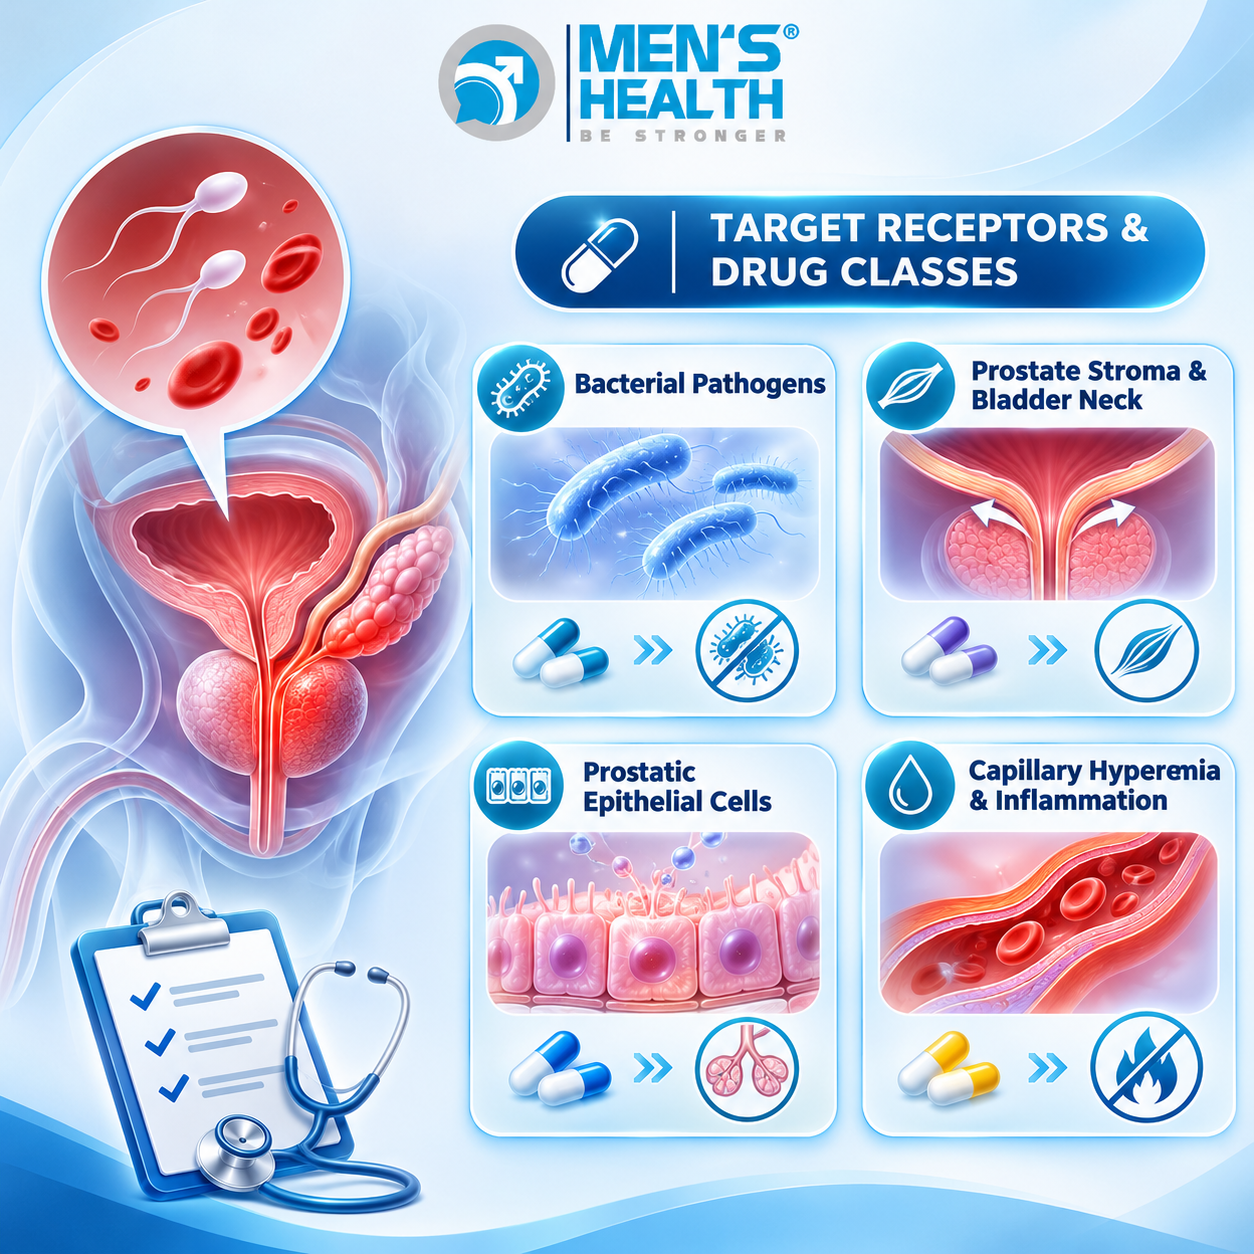
Core Pharmacological Classes
Targeted Antibiotic Therapy
- Mechanism of Action: Highly lipophilic antimicrobial agents capable of crossing the blood-prostate barrier to achieve bactericidal concentrations in prostatic fluid and seminal vesicle tissue.
- Representative Agents: Fluoroquinolones (Ciprofloxacin, Levofloxacin), Doxycycline, Macrolides (Azithromycin).
- Indications: Confirmed bacterial prostatitis, seminal vesiculitis, or STI-associated urethritis. Extended therapy (2 to 4 weeks) is often required.
Non-Steroidal Anti-Inflammatory Drugs (NSAIDs)
- Mechanism of Action: Inhibition of cyclooxygenase (COX-2) enzymes, decreasing prostaglandin synthesis within congested pelvic tissues.
- Representative Agents: Celecoxib, Meloxicam, Ibuprofen.
- Indications: Non-bacterial inflammatory vesiculitis or pelvic pain syndromes, reducing edema and mucosal capillary fragility.
Alpha-1 Adrenoceptor Antagonists (-Blockers)
- Mechanism of Action: Selective blockade of -adrenoceptors in the prostate stroma and bladder neck, reducing intraprostatic voiding pressure and ejaculatory duct reflux.
- Representative Agents: Tamsulosin, Silodosin, Alfuzosin.
- Indications: Co-existing lower urinary tract symptoms (LUTS) or ejaculatory duct hypertension.
5-Alpha Reductase Inhibitors (5-ARIs)
- Mechanism of Action: Inhibits conversion of testosterone to dihydrotestosterone (DHT), inducing prostatic epithelial apoptosis and suppressing subepithelial microvessel density.
- Representative Agents: Finasteride, Dutasteride.
- Indications: Persistent, refractory hematospermia associated with benign prostatic enlargement or friable prostatic urethral vascularity.
7. Professional Care at Men’s Health Center and Men’s Health Pharmacy
Managing male genital tract bleeding requires accurate diagnostic differentiation, risk stratification, and specialized clinical pharmacy care.
Men’s Health Pharmacy, an integral unit within the Men’s Health Center ecosystem founded by Dr. Tra Anh Duy (MD, PhD, Spec. II), provides specialized clinical pharmacy services for male reproductive and urological health. At Men’s Health, patients receive tailored consultations from experienced urologists and clinical pharmacists to ensure that prescribed therapeutic regimens – including lipid-soluble antimicrobials, anti-inflammatory agents, and -blockers – are calibrated precisely to diagnostic findings. The facility maintains strict clinical safety standards, individual privacy, absolute confidentiality, and evidence-based practice across all phases of patient evaluation and follow-up care.

8. Lifestyle Modifications and Preventive Measures
- Fluid Optimization: Maintain daily fluid intake () to preserve lower tract flushing and minimize urinary concentration.
- Ejaculatory Hygiene: Maintain regular, non-strenuous ejaculatory intervals to avoid seminal vesicle stasis and fluid hyper-concentration.
- Avoidance of Pelvic Trauma: Minimize prolonged, unpadded bicycle riding or straddle activities that strain the perineum.
- Barrier Protection: Utilize condoms during non-monogamous sexual contact to reduce the risk of sexually transmitted infections.
9. Common Clinical Pitfalls in Differential Evaluation
- Confusing Hematospermia with Gross Hematuria: Failing to confirm whether blood is present exclusively in ejaculatory fluid or throughout the voided urine stream, leading to misdirected diagnostic testing.
- Over-investigating Young, Low-Risk Patients: Subjecting young men with isolated, transient hematospermia to invasive endoscopic or complex radiologic procedures without first screening for common infectious etiologies.
- Under-evaluating Older Patients: Presuming persistent hematospermia in a male aged years is benign without evaluating serum PSA levels or ordering pelvic mpMRI.
- Inadequate Antibiotic Duration: Prescribing short, 3-to-5-day courses of standard oral antibiotics for deep pelvic infections (prostatitis/vesiculitis), leading to incomplete bacterial clearance and early recurrence.
10. Frequently Asked Questions
How can a patient tell the difference between blood in semen and blood in urine?
Blood in semen appears exclusively during or immediately following ejaculation, turning the ejaculate bright red, pink, dark brown, or rusty. Blood in urine (hematuria) appears during micturition, turning the urine pink, red, or cola-colored.
What is pseudo-hematospermia?
Pseudo-hematospermia occurs when seminal fluid appears blood-stained due to external blood from a sexual partner (such as menstrual blood or cervical/vaginal lesions) rather than an anatomical issue within the male reproductive tract.
Is hematospermia usually a sign of prostate cancer?
No. Over of hematospermia cases stem from benign causes such as infection, inflammation, or minor capillary micro-trauma. However, in men over 50 years of age, persistent hematospermia warrants evaluation for underlying prostate adenocarcinoma.
When should diagnostic imaging (like TRUS or mpMRI) be ordered?
Diagnostic imaging is indicated when hematospermia is persistent (lasting weeks), recurrent, associated with red flag symptoms (such as pain, weight loss, or gross hematuria), or when occurring in men over 50 years with elevated serum PSA levels.
Can an untreated sexually transmitted infection cause blood in semen?
Yes. Pathogens such as Chlamydia trachomatis, Neisseria gonorrhoeae, and Ureaplasma species cause urethritis, prostatitis, and vesiculitis, leading to mucosal inflammation, capillary fragility, and hematospermia.
Conclusion and Expert Clinical Advice
Hematospermia and male genital tract bleeding require a structured clinical diagnostic pathway to differentiate benign, self-limiting etiologies from serious urological conditions like hematuria, urethrorrhagia, or prostate carcinoma. Establishing the exact timing of blood appearance relative to micturition and ejaculation – supported by urinalysis, STI screening, PSA testing, and pelvic imaging – ensures accurate management.
Patients noticing blood in their seminal fluid should avoid self-diagnosis or unprescribed antibiotic usage. Seeking direct clinical evaluation at a specialized urological facility such as the Men’s Health Center guarantees precise diagnostic differentiation, specialist physician management, and dedicated clinical pharmacy support for long-term reproductive and urological health.