Hematospermia – the macroscopic or microscopic presence of blood in the ejaculatory fluid – and male genital tract hemorrhage are clinically significant presentations that often provoke severe patient anxiety. While the vast majority of cases stem from benign, self-limiting inflammatory or infectious processes, persistent, recurrent, or high-volume bleeding can signal structural vascular malformations, obstructive ductal lesions, or underlying urogenital malignancies. Determining the precise clinical juncture at which conservative medical management must transition to procedural decompression or definitive surgical intervention is critical to preserving fertility, preventing irreversible structural damage, and optimizing patient outcomes.
1. Clinical Overview, Definitions, and Pathophysiological Rationale
What is Hematospermia and Male Genital Tract Bleeding?
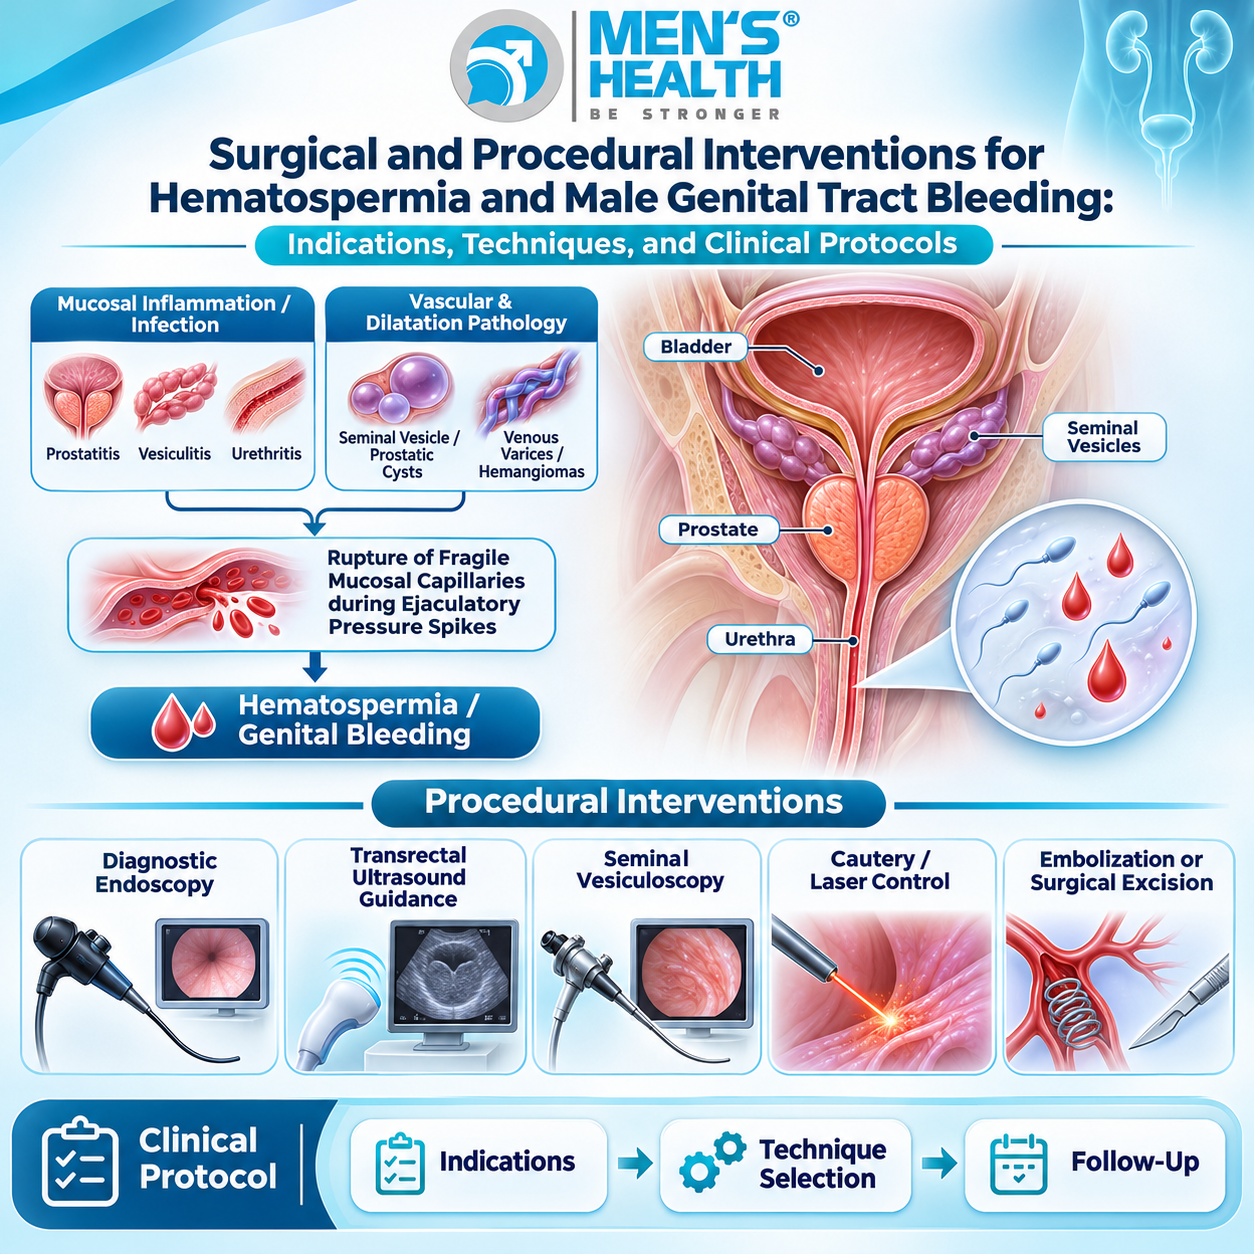
Hematospermia (also termed hemospermia) is defined by the International Continence Society (ICS) and standard urological guidelines as the presence of blood in semen. Visually, it ranges from fresh, bright-red fluid streaks to dark brown or rust-colored discoloration representing oxidized intra-vesicular blood. Male genital tract bleeding encompasses any vascular breach along the complex anatomical pathways responsible for seminal production, maturation, storage, and transport – including the testes, epididymides, vasa deferentia, seminal vesicles, prostate gland, bulbourethral (Cowper’s) glands, and prostatic urethra.
Pathophysiological Cascade and Mechanical Dynamics
Ejaculatory fluid comprises fractional contributions from the seminal vesicles (60-70%), prostate gland (20-30%), testes/epididymides (5%), and bulbourethral glands (5%). Vascular disruption occurs via three main pathophysiological mechanisms:
- Mucosal Hyperemia and Capillary Fragility: Acute or chronic inflammatory responses within the prostate or seminal vesicles induce micro-vascular engorgement, tissue edema, and subepithelial capillary fragility. The rapid, dynamic hydraulic pressure spike generated during ejaculatory smooth muscle contraction ruptures these fragile vessels.
- Ductal Obstruction, Intra-vesicular Stasis, and Cystic Distension: Intra-prostatic cysts, ejaculatory duct calcifications, or luminal strictures cause proximal glandular distension, ischemic mucosal thinning, and secondary micro-hemorrhage into stored seminal fluid.
- Neoplastic Neoangiogenesis and Vascular Dysplasia: Malignant proliferation (e.g., prostatic or seminal vesicle adenocarcinoma) upregulates vascular endothelial growth factor (VEGF), generating irregular, thin-walled micro-vessels prone to spontaneous structural failure. Alternatively, benign vascular malformations (hemangiomas, prostatic urethral varices) bleed intermittently under normal pelvic physiological pressures.
2. Clinical Indications for Procedural and Surgical Interventions
Determining when conservative or pharmacological management is insufficient requires clear risk stratification. Procedural or endourological intervention is indicated in specific refractory or high-risk clinical scenarios.
Absolute and Relative Indications
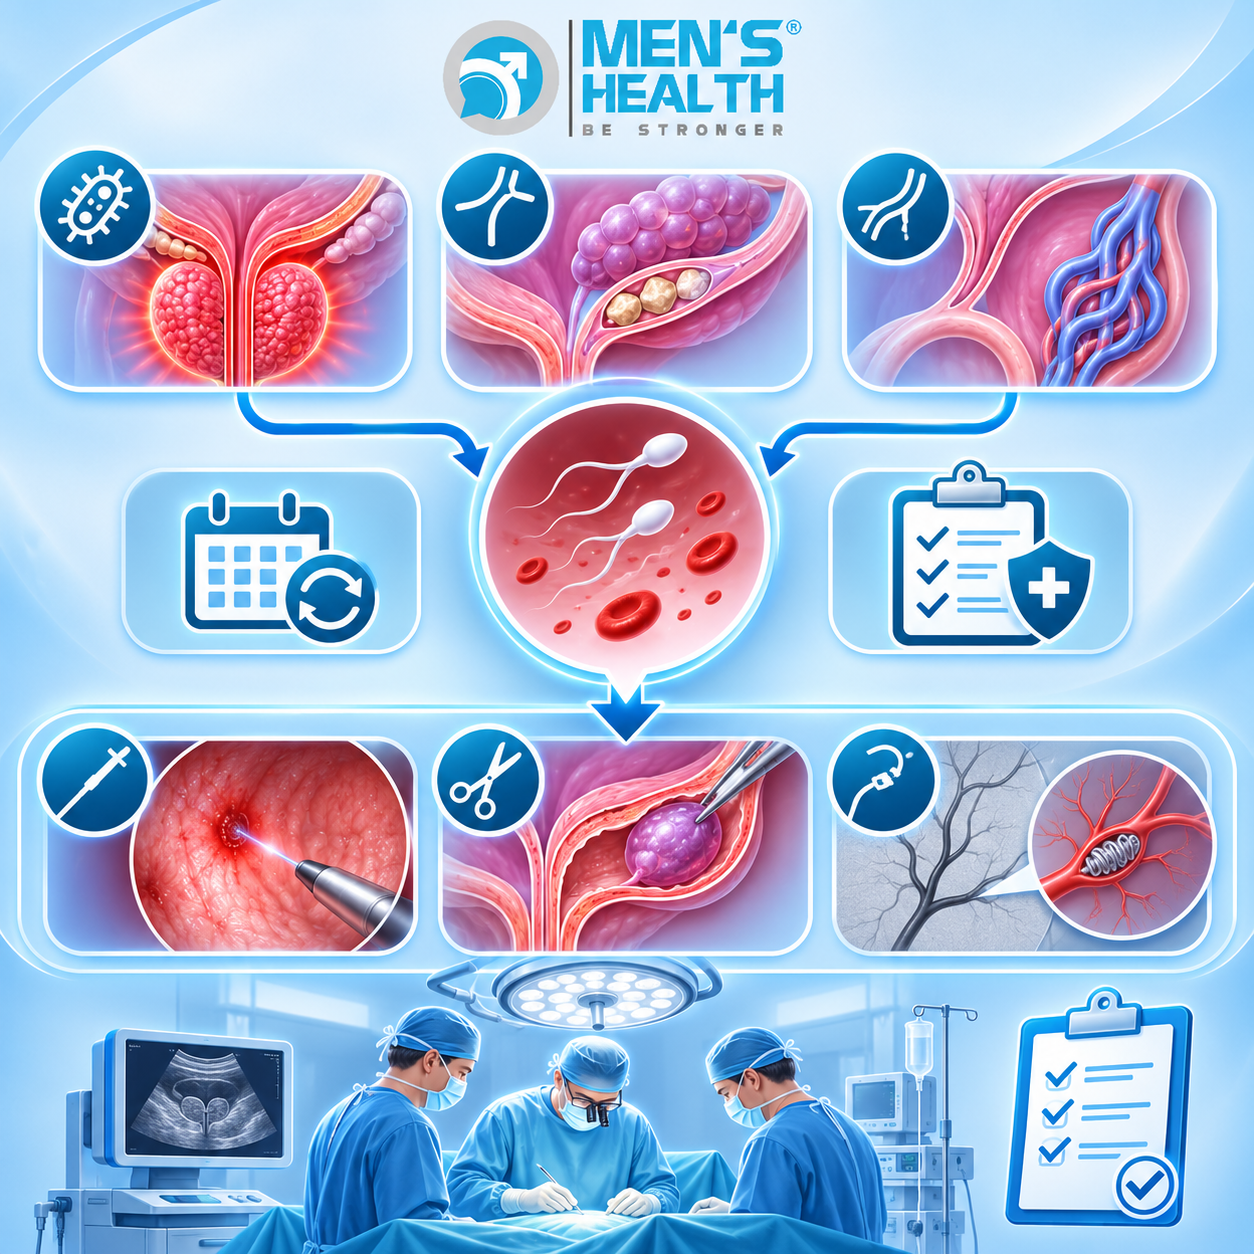
- Refractory or Chronic Recurrent Bleeding: Persistent hematospermia lasting >8-12 weeks that fails to respond to targeted antimicrobial, anti-inflammatory, or 5α-reductase inhibitor therapy.
- Ejaculatory Duct Obstruction (EDO): Confirmed ductal occlusion secondary to strictures, calculi, or cysts accompanied by painful ejaculation, low-volume ejaculate (<1.5 mL), and severe seminal vesicle distension (transverse diameter >15 mm).
- Symptomatic Pelvic and Prostatic Cysts: Large Müllerian duct cysts, prostatic utricle cysts, or seminal vesicle cysts causing secondary voiding symptoms, chronic pelvic pain, or persistent bleeding.
- Vascular Lesions of the Lower Urinary Tract: Direct visualization or imaging confirmation of bleeding prostatic urethral varices, hemangiomas, or arteriovenous malformations near the verumontanum.
- Confirmed or Highly Suspected Urogenital Malignancy: Multiparametric MRI (mpMRI) identifying PIRADS 4 or 5 lesions, or tissue biopsies confirming prostate adenocarcinoma or seminal vesicle neoplasms requiring definitive oncological surgery.
3. Surgical and Procedural Modalities for Male Genital Tract Bleeding
When procedural intervention is warranted, modalities range from minimally invasive endourological techniques to advanced image-guided embolization and reconstructive surgery.
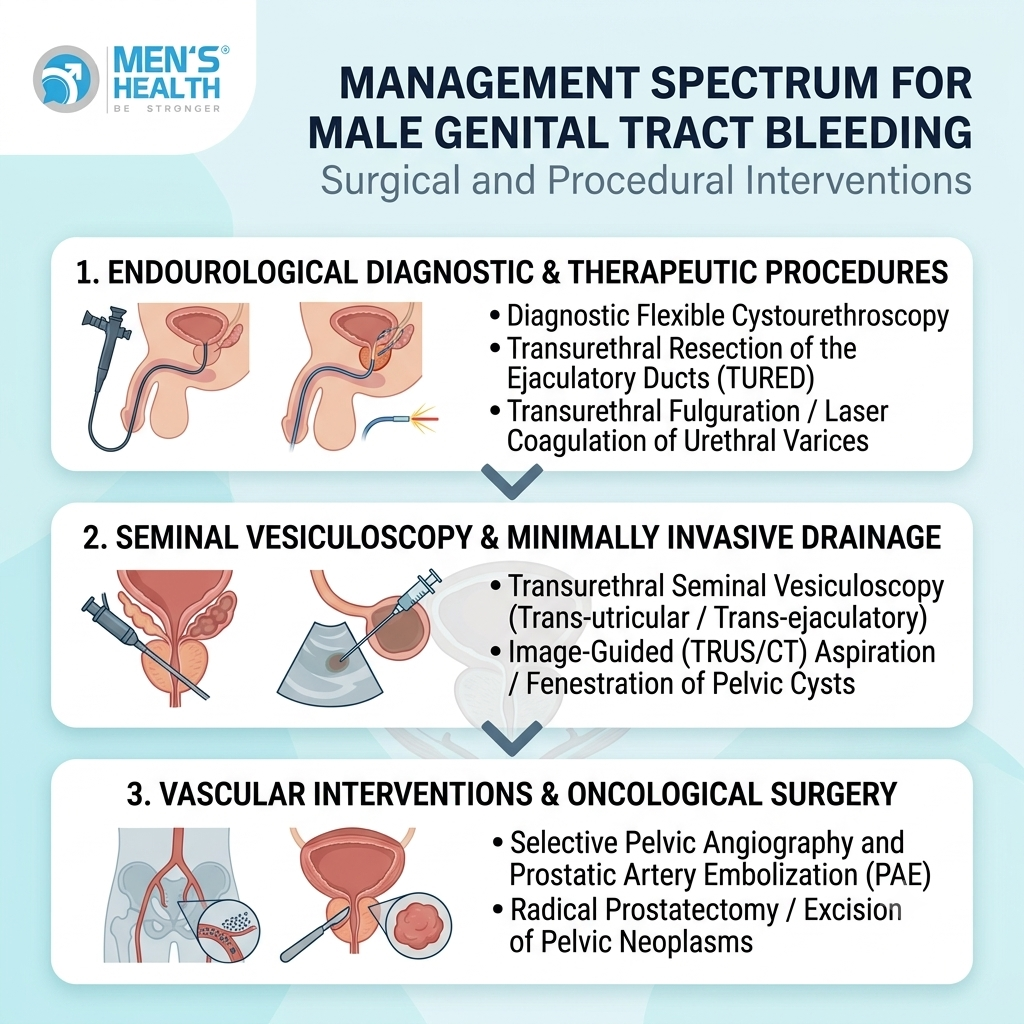
1. Transurethral Resection of the Ejaculatory Ducts (TURED)
- Technique: Electrosurgical or laser resection of the verumontanum and roof of the ejaculatory ducts under direct endoscopic visualization.
- Mechanism & Goal: Relieves intra-vesicular and ductal hypertension caused by distal strictures, cysts, or lithiasis. Decompresses stagnant, blood-stained fluid and restores seminal flow.
- Clinical Efficacy: High success rate ($>80\%$) in resolving obstructive hematospermia and improving seminal parameters in infertile men with EDO.
2. Transurethral Seminal Vesiculoscopy (TUSV)
- Technique: Utilization of ultra-thin semirigid ureteroscopes (4.5 – 7.5 Fr) introduced endoscopically through the prostatic utricle or ejaculatory duct orifices into the lumen of the seminal vesicles.
- Mechanism & Goal: Allows direct endoscopic visualization of the seminal vesicle mucosa, clearance of retained blood clots, extraction of seminal vesicle calculi via micro-baskets, and targeted mucosal fulguration or drug instillation (e.g., anti-inflammatory/antibiotic lavage).
- Clinical Role: Represents the modern diagnostic and therapeutic gold standard for refractory, unexplained seminal vesicle hemorrhage.
3. Endoscopic Laser Coagulation and Electrocautery
- Technique: Application of Holmium:YAG, Thulium, or KTP laser energy, or monopolar/bipolar electrocautery, to visible vascular anomalies along the prostatic urethra or verumontanum.
- Mechanism & Goal: Achieves immediate hemostasis and ablation of friable urethral hemangiomas, mucosal varices, or granulation tissue responsible for recurrent post-ejaculatory urethrorrhagia.
4. Transrectal Ultrasound (TRUS)-Guided Cyst Aspiration and Fenestration
- Technique: Ultrasound-guided transrectal or transperineal needle puncture, aspiration, and sclerotherapy (e.g., with absolute alcohol or doxycycline), or transurethral endoscopic unroofing/fenestration of prostatic or Müllerian duct cysts.
- Mechanism & Goal: Evacuates high-tension cystic fluid, collapses the cyst wall, and eliminates chronic stasis driving recurrent micro-hemorrhage.
5. Selective Pelvic Angiography and Prostatic Artery Embolization (PAE)
- Technique: Endovascular catheterization of the internal iliac artery branch vessels and selective prostatic/vesicular arteries, followed by micro-particle embolization.
- Mechanism & Goal: Devascularizes extensive arteriovenous malformations or severe refractory prostatic vascular bleeding when endoscopic approaches are unfeasible or fail.
4. Comparative Analysis of Surgical and Procedural Options
| Procedural Modality | Primary Clinical Indication | Mechanism of Action | Key Clinical Benefits | Potential Risks & Complications |
| Diagnostic Flexible Cystoscopy | Unexplained hematospermia with hematuria | Direct luminal inspection | Outpatient procedure, identifies urethral lesions | Mild dysuria, transient hematuria, UTI risk |
| TURED | Ejaculatory Duct Obstruction / Cysts | Electrosurgical unroofing of ducts | Relieves ductal tension, improves fertility metrics | Retrograde ejaculation, urine reflux into vesicles |
| Seminal Vesiculoscopy (TUSV) | Refractory seminal vesicle hemorrhage | Direct endoscopic inspection & lavage | Direct visualization, clot clearance, stone extraction | Ejaculatory duct trauma, transient epididymitis |
| Laser / Cautery Ablation | Prostatic urethral varices / Hemangiomas | Photothermal tissue coagulation | Rapid hemostasis, low tissue thermal injury | Urethral stricture, transient dysuria |
| TRUS-Guided Fenestration | Intra-prostatic & Müllerian duct cysts | Percutaneous or transurethral unroofing | Collapses cyst cavity, eliminates stasis | Cyst recurrence, pelvic infection / abscess |
| Prostatic Artery Embolization | Massive pelvic vascular malformations | Endovascular micro-particle occlusion | Minimally invasive control of severe vascular lesions | Post-embolization syndrome, non-target embolization |
5. Comprehensive Pre-Surgical Diagnostic Protocol
Prior to embarking on invasive procedural management, a rigorous diagnostic workup is mandatory to localize the bleeding site, exclude active infection, and map pelvic anatomy.
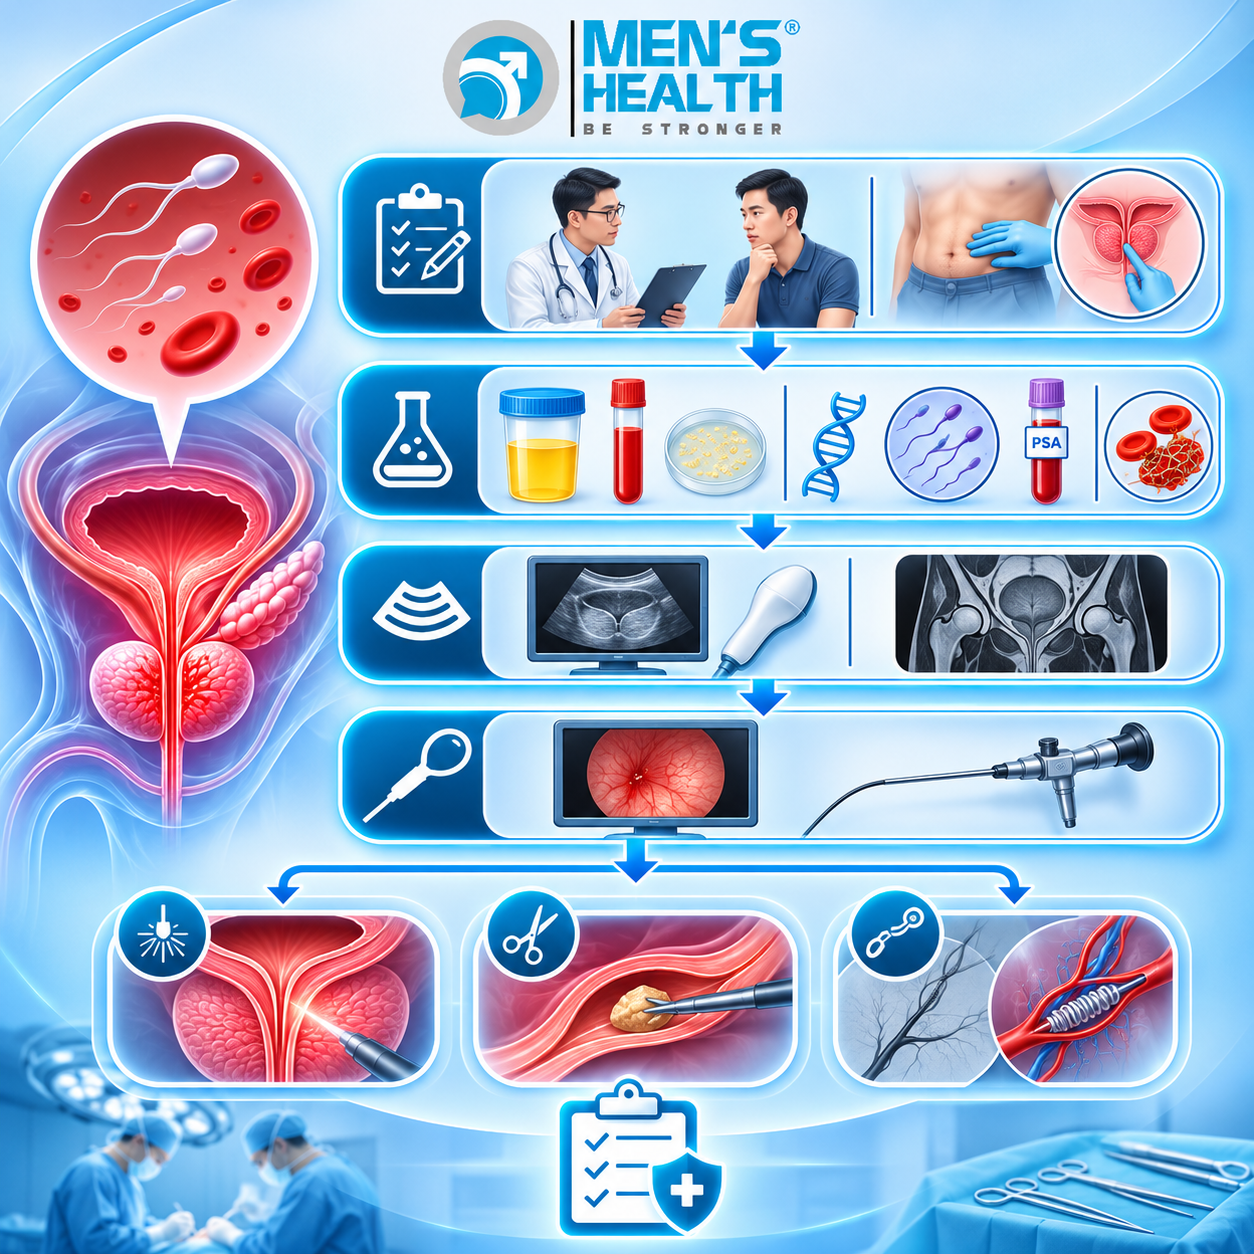
- Detailed History and Physical Examination: Documentation of exact bleeding duration, fluid color (bright red vs. dark brown), relationship to micturition versus ejaculation, recent transrectal procedures (e.g., prostate biopsy), and DRE assessment of prostate architecture.
- Laboratory Diagnostics: Urinalysis and culture rule out bacterial cystitis; NAAT screens for STIs (Chlamydia trachomatis, Neisseria gonorrhoeae); serum PSA screens for prostatic malignancy in men >45-50 years; coagulation panels evaluate bleeding diatheses.
- Transrectal Ultrasound (TRUS): Evaluates seminal vesicle volume, intra-prostatic cysts, and ejaculatory duct calcifications.
- Multiparametric Pelvic MRI (mpMRI): The non-invasive gold standard for soft-tissue characterization. mpMRI detects subtle seminal vesicle hemorrhage, ductal anomalies, and focal prostate cancer (PIRADS grading).
- Flexible Cystourethroscopy: Direct endoscopic inspection of the anterior/posterior urethra, verumontanum, and bladder neck. Mandatory when recurrent hematospermia is paired with gross hematuria or suspected urethral vascular lesions.
6. Differential Diagnosis Spectrum
Differentiating true hematospermia from other lower urinary tract and genital bleeding manifestations is essential prior to planning procedural interventions.
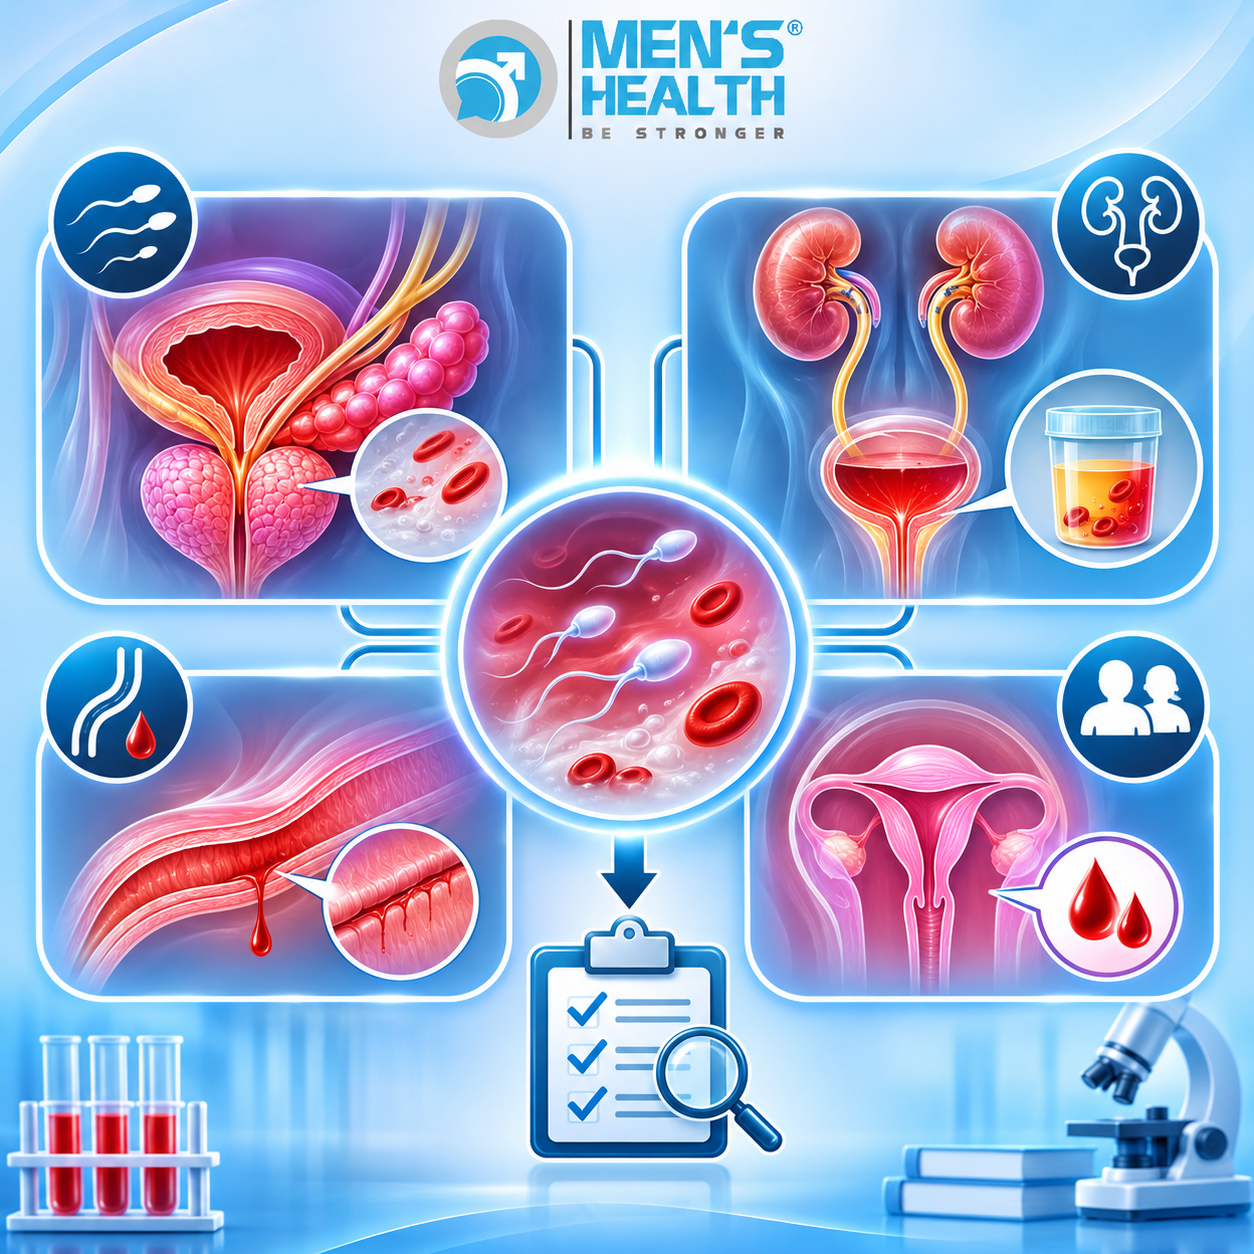
Symptom Comparison Matrix
| Clinical Condition | Primary Bleeding Source | Timing of Blood Appearance | Diagnostic Differentiation |
| True Hematospermia | Seminal vesicles, prostate, vasa | Admixed directly within semen | TRUS/mpMRI shows seminal vesicle/prostate pathology |
| Gross Hematuria | Kidneys, ureters, bladder | Present throughout voided urine stream | Microscopic pyuria/hematuria; cystoscopy shows mucosal lesions |
| Urethrorrhagia | Anterior or bulbar urethra | Spontaneous discharge between voids | Urethroscopy confirms anterior urethral lesion or stricture |
| Prostatic Abscess | Prostatic parenchyma | Present in both urine and semen | DRE shows tender, fluctuant prostate; pelvic US reveals cavity |
| Pseudo-Hematospermia | Female partner genital tract | Stained exteriorly post-coitus | Normal male urinalysis and sterile semen examination |
7. Pharmacological Management Strategies Pre- and Post-Procedure
Targeted medical therapy is essential before considering surgery and as supportive care post-procedure.
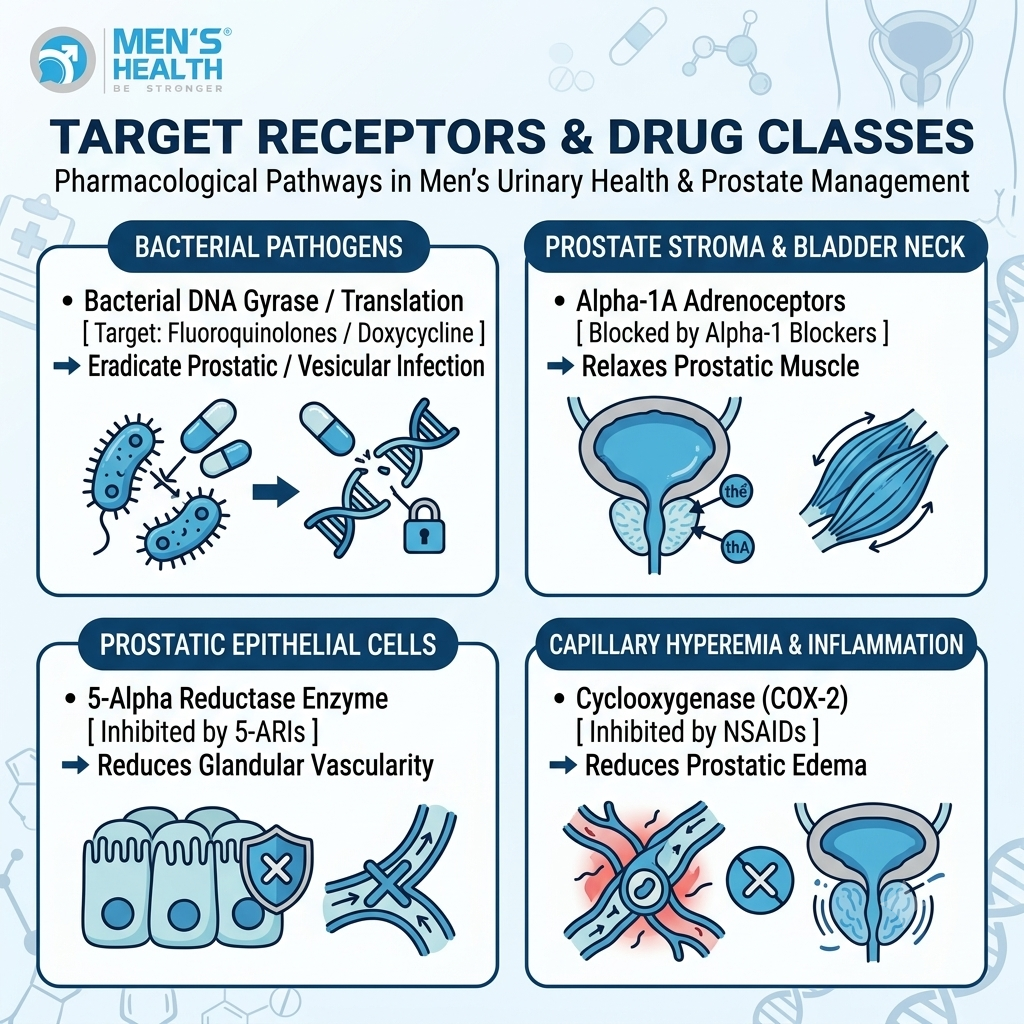
Core Pharmacological Classes
- Targeted Lipid-Soluble Antibiotics (e.g., Fluoroquinolones, Doxycycline): Cross the blood-prostate barrier to achieve therapeutic concentrations within prostatic fluid and seminal vesicle tissue. Administered pre-operatively to sterilize the genitourinary tract and prevent post-procedural sepsis.
- Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) (e.g., Celecoxib, Meloxicam): Inhibit COX-2 enzymes, decreasing prostaglandin synthesis, tissue edema, and post-procedural pain.
- Alpha-1 Adrenoceptor Antagonists (e.g., Tamsulosin, Silodosin): Block α1A-adrenoceptors in the prostate stroma and bladder neck, lowering intra-prostatic voiding pressure, facilitating smooth ejaculate discharge, and preventing post-procedural urinary retention.
- 5-Alpha Reductase Inhibitors (5-ARIs) (e.g., Finasteride, Dutasteride): Suppress subepithelial microvessel density in prostatic tissue, serving as an effective medical therapy to reduce bleeding prior to or following endourological procedures.
8. Professional Care at Men’s Health Center and Men’s Health Pharmacy
Navigating the evaluation and surgical management of male genital tract bleeding requires structured medical diagnosis, accurate risk stratification, and specialized clinical pharmacy care.
Men’s Health Pharmacy, an integral unit within the Men’s Health Center ecosystem founded by Dr. Tra Anh Duy (MD, PhD, Spec. II), provides specialized clinical pharmacy services for male reproductive and urological health. At Men’s Health, patients receive tailored consultations from experienced urologists and clinical pharmacists to ensure that prescribed therapeutic regimens—including lipid-soluble antimicrobials, anti-inflammatory agents, and $\alpha_1$-blockers—are calibrated precisely to pre-procedural and post-operative needs. The facility maintains strict clinical safety standards, individual privacy, absolute confidentiality, and evidence-based practice across all phases of patient evaluation and follow-up care.

9. Lifestyle Modifications and Post-Procedural Recovery Guidelines
- Adequate Hydration: Maintain a daily fluid intake of 1.5 – 2.0 L to ensure regular lower tract flushing and reduce urinary concentration.
- Post-Procedural Pelvic Rest: Abstain from sexual activity and strenuous physical exertion for 2 to 4 weeks following endourological procedures (TURED or vesiculoscopy) to allow mucosal re-epithelialization.
- Avoidance of Perineal Trauma: Limit prolonged, unpadded bicycle riding or straddle activities that exert mechanical pressure on pelvic structures.
- Safe Sexual Practices: Utilize condoms during non-monogamous sexual contact to prevent sexually transmitted infection acquisition and recurrent inflammation.
10. Common Clinical Pitfalls in Managing Procedural Interventions
- Performing Invasive Surgery Without Pelvic MRI Mapping: Attempting endourological procedures without pre-operative mpMRI mapping risks missing focal prostate cancer or failing to localize complex cystic anatomy.
- Failing to Warn Patients About Retrograde Ejaculation Post-TURED: Resecting the verumontanum without counseling young, fertile men regarding the high risk of retrograde ejaculation can result in unexpected iatrogenic subfertility.
- Overtreating Transient Post-Biopsy Hematospermia: Subjecting patients to invasive vesiculoscopy or TURED for self-limiting blood in semen following transrectal prostate biopsy, which typically resolves spontaneously over 4 to 8 weeks.
- Inadequate Pre-Procedural Antibiotic Prophylaxis: Operating on distended, infected seminal vesicles without broad-spectrum lipid-soluble antibiotic coverage, risking severe post-procedural pelvic sepsis or epididymo-orchitis.
11. Frequently Asked Questions About Surgical Interventions for Hematospermia
When is surgery or a procedure necessary for blood in semen?
Procedural or surgical intervention is necessary when hematospermia is persistent (lasting >8-12 weeks), recurrent, associated with ejaculatory duct obstruction, large symptomatic pelvic cysts, visible urethral vascular malformations, or confirmed urogenital malignancy.
What is Transurethral Resection of the Ejaculatory Ducts (TURED)?
TURED is a minimally invasive endourological procedure where a urologist resects obstructive tissue or unroofs cysts at the verumontanum under endoscopic view. It decompresses blocked seminal vesicles and restores normal semen evacuation.
How does Seminal Vesiculoscopy (TUSV) treat refractory hematospermia?
Seminal Vesiculoscopy uses an ultra-thin endoscope introduced directly into the seminal vesicles. It allows direct visualization of the mucosal lining, clearance of old blood clots, extraction of calculi, and targeted laser coagulation of bleeding vessels.
Can procedures for hematospermia affect male fertility or ejaculation?
Yes. While procedures like TURED can improve fertility by relieving ductal obstruction in men with oligo-azoospermia, resecting the bladder neck or verumontanum carries a risk of retrograde ejaculation (where semen flows back into the bladder during orgasm).
How long is the recovery period after an endourological procedure for hematospermia?
Most endoscopic procedures (such as vesiculoscopy or TURED) are outpatient or short-stay procedures. Patients typically require 2 to 4 weeks of pelvic and sexual rest to ensure complete mucosal healing and prevent recurrent bleeding.
Conclusion and Expert Clinical Advice
Surgical and procedural interventions play a vital role in managing refractory, recurrent, or obstructive hematospermia and male genital tract bleeding. Through advanced diagnostic pathways – including pelvic mpMRI, transrectal ultrasonography, and flexible cystoscopy – urologists can accurately identify structural causes like ejaculatory duct obstruction, pelvic cysts, or urethral varices. Minimally invasive procedures such as Seminal Vesiculoscopy and TURED offer excellent therapeutic efficacy while preserving patient safety.
Patients experiencing persistent or recurrent blood in their ejaculate should avoid self-diagnosis and refrain from delaying specialized medical evaluation. Seeking clinical care at an established urological facility such as the Men’s Health Center guarantees precise diagnostic assessment, expert surgical management, and dedicated clinical pharmacy support for long-term urological and reproductive health.