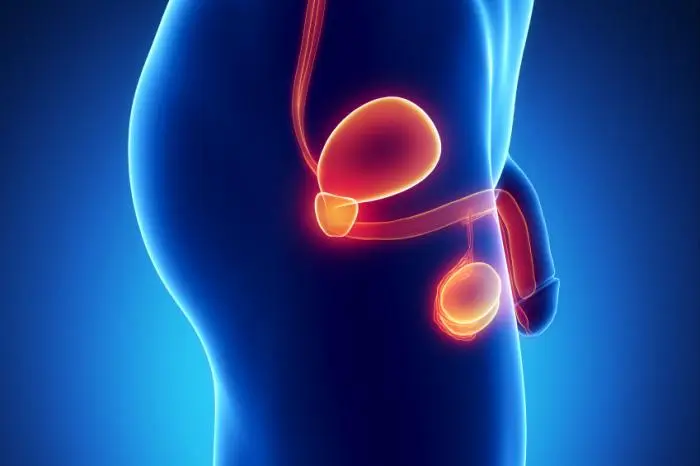
Hematospermia (also termed hemospermia) – the presence of macroscopic or microscopic blood in the ejaculatory fluid – is a clinically distressing manifestation for male patients. While frequently a benign, self-limiting phenomenon linked to subclinical pelvic inflammation, its potential recurrence raises significant concern regarding unaddressed lower urinary tract pathology, structural vascular lesions, persistent infectious foci, or occult urogenital malignancies.
1. Clinical Overview and Mechanisms of Recurrence
What is Hematospermia and Male Genital Tract Bleeding?
Hematospermia is defined by the International Continence Society (ICS) and standard urological guidelines as the presence of blood in semen, ranging from fresh bright-red streaks to oxidized dark-brown or rust-colored staining. It signifies vascular wall disruption anywhere along the multi-glandular pathway of semen production, storage, and transport – including the testes, epididymides, vasa deferentia, seminal vesicles, prostate gland, and prostatic urethra.
Pathophysiological Drivers of Recurrence
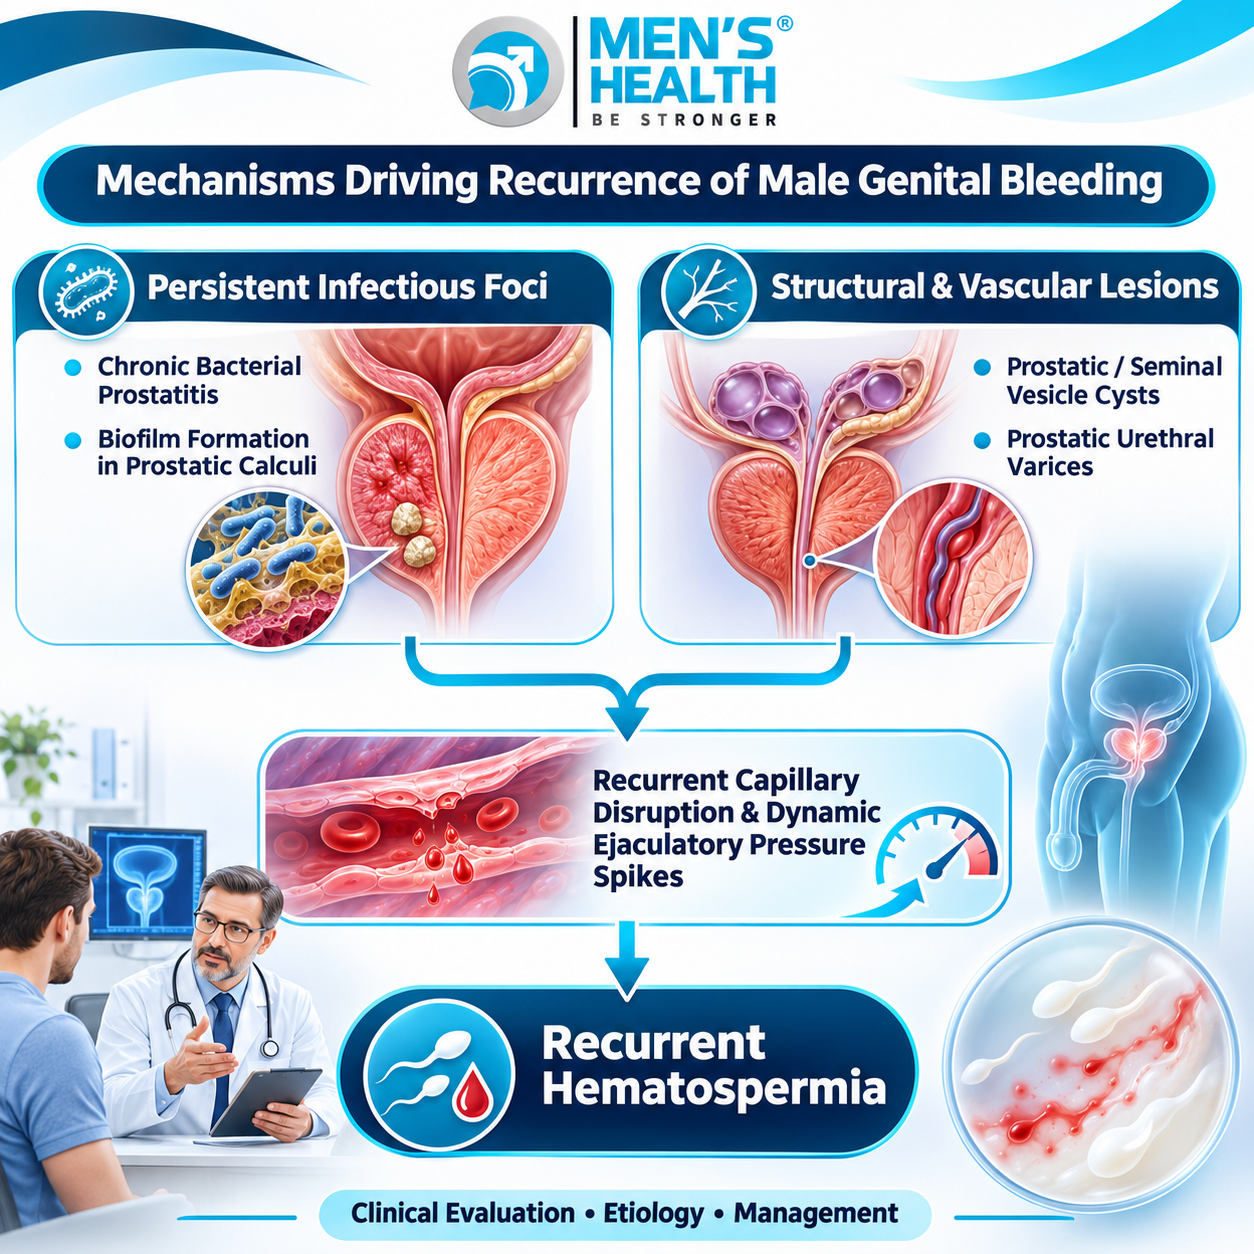
Semen comprises fluid originating from the seminal vesicles (60-70%), prostate gland (20-30%), and testes/epididymides (5%). The recurrence of bleeding post-treatment stems primarily from three pathological mechanisms:
- Incomplete Eradication of Deep Glandular Infection: Bacterial biofilms within prostatic micro-calculi or chronic seminal vesiculitis often evade short-course antimicrobial therapy, leading to recurrent mucosal hyperemia and capillary failure under ejaculatory hydraulic stress.
- Unresolved Structural and Cystic Anomalies: Congenital or acquired ejaculatory duct cysts, Müllerian duct remnants, or prostatic utricle cysts cause persistent proximal fluid stasis, mucosal stretching, and recurrent micro-hemorrhage.
- Vascular and Neoplastic Persistence: Arteriovenous malformations, urethral hemangiomas, or undiagnosed low-grade prostate adenocarcinoma express tumor angiogenesis factors (e.g., VEGF), generating fragile vessels prone to repeated rupture.
2. Etiology and Predisposition Behind Recurrent Genital Bleeding
Understanding why male genital bleeding recurs requires evaluating distinct anatomical and systemic causes:
Infectious and Inflammatory Recurrence
- Chronic Bacterial Prostatitis (CBP) and Vesiculitis: Recurrent infection by persistent pathogens (Escherichia coli, Enterococcus faecalis, Chlamydia trachomatis) causing chronic pelvic congestion.
- Calcified Prostatic Lithiasis: Prostatic calculi act as persistent mechanical irritants against acinar epithelium during ejaculatory muscular contractions.
Structural, Cystic, and Obstructive Etiologies
- Ejaculatory Duct Obstruction (EDO): Partial ductal strictures or cysts cause recurrent intra-vesicular hypertension and localized vascular distension.
- Prostatic Urethral Varices and Hemangiomas: Engorged venous plexus structures near the verumontanum that bleed intermittently upon pelvic vascular engorgement.
Oncological Factors
- Prostate Adenocarcinoma: The primary malignant concern in men aged >50 years presenting with persistent or recurrent hematospermia.
- Seminal Vesicle and Testicular Neoplasms: Rare primary carcinomas or germ cell tumors causing progressive tissue erosion.
Systemic and Iatrogenic Factors
- Uncontrolled Systemic Hypertension: Fluctuating, severe arterial pressure increases capillary shear stress in pelvic vascular beds.
- Coagulopathies and Anticoagulant Pharmacotherapy: Ongoing use of antiplatelet agents (aspirin, clopidogrel) or oral anticoagulants (warfarin, DOACs) lowers the threshold for micro-vascular bleeding.
3. Symptom Presentation and Red Flag Indicators
Visual and Clinical Characteristics
The presentation of recurrent hematospermia varies based on the bleeding source and transit duration:
- Bright Red / Fresh Blood: Indicates active, acute hemorrhage from the distal tract (e.g., prostatic urethra or verumontanum).
- Dark Brown / Rust-Colored / Clotted Fluid: Represents old, oxidized intra-vesicular blood cleared gradually over multiple voiding and ejaculatory cycles.
Red Flag Symptoms Requiring Immediate Specialist Assessment
The presence of any of the following clinical indicators alongside recurrent hematospermia warrants immediate, high-priority specialist evaluation:
- Patient age ≥ 50 years with unprovoked, persistent, or recurrent hematospermia.
- Concurrent gross hematuria (macroscopic blood in voided urine).
- Palpable prostatic nodules on Digital Rectal Examination (DRE) or discrete testicular masses.
- Systemic red flags: Unexplained weight loss, night sweats, persistent pelvic or back pain, or high fever with rigors.
- Symptom duration exceeding 4–8 weeks or progressive escalation in bleeding volume.
4. Comprehensive Diagnostic Pathways for Recurrent Hematospermia
Re-evaluating a patient with recurrent genital bleeding requires moving systematically from non-invasive screening to specialized imaging and endourological visualization.

- Detailed History and Physical Examination: Documenting exact bleeding duration, color, relationship to voiding, recent transrectal procedures (e.g., prostate biopsy), and DRE assessment of prostate architecture.
- Laboratory Diagnostics: Urinalysis and culture rule out bacterial cystitis; NAAT screens for STIs (C. trachomatis, N. gonorrhoeae); serum PSA screens for prostatic malignancy in men >45-50 years; coagulation panels evaluate bleeding diatheses.
- Transrectal Ultrasound (TRUS): Evaluates seminal vesicle enlargement, intra-prostatic cysts, and ductal calcifications.
- Multiparametric Pelvic MRI (mpMRI): The non-invasive gold standard for soft-tissue characterization. mpMRI detects subtle seminal vesicle hemorrhage, ductal anomalies, and focal prostate cancer (PIRADS grading).
- Flexible Cystourethroscopy: Direct endoscopic inspection of the anterior/posterior urethra, verumontanum, and bladder neck. Mandatory when recurrent hematospermia is paired with gross hematuria or suspected urethral vascular lesions.
5. Diagnostic Testing Matrix
| Diagnostic Test | Primary Clinical Objective | Key Diagnostic Value in Recurrence |
| Digital Rectal Exam (DRE) | Physical evaluation of prostate architecture | Identifies prostatic tenderness, asymmetry, or malignant nodules |
| Urinalysis & NAAT | Infectious screening | Excludes persistent bacterial cystitis, urethritis, or STI pathogens |
| Serum PSA Test | Tumor screening | Elevated levels indicate potential prostate carcinoma or severe inflammation |
| Transrectal Ultrasound (TRUS) | Structural evaluation | Visualizes seminal vesicle enlargement, ejaculatory duct cysts, or calculi |
| Pelvic mpMRI | High-resolution soft-tissue imaging | Gold standard for detecting occult prostate cancer, hemorrhage, or malformations |
| Flexible Cystoscopy | Direct luminal visualization | Detects urethral varices, hemangiomas, strictures, or bladder neck lesions |
6. Pharmacological Management Strategies for Recurrent Bleeding
When diagnostic workup establishes the underlying cause of recurrence, targeted medical therapy is prescribed.
Core Pharmacological Classes
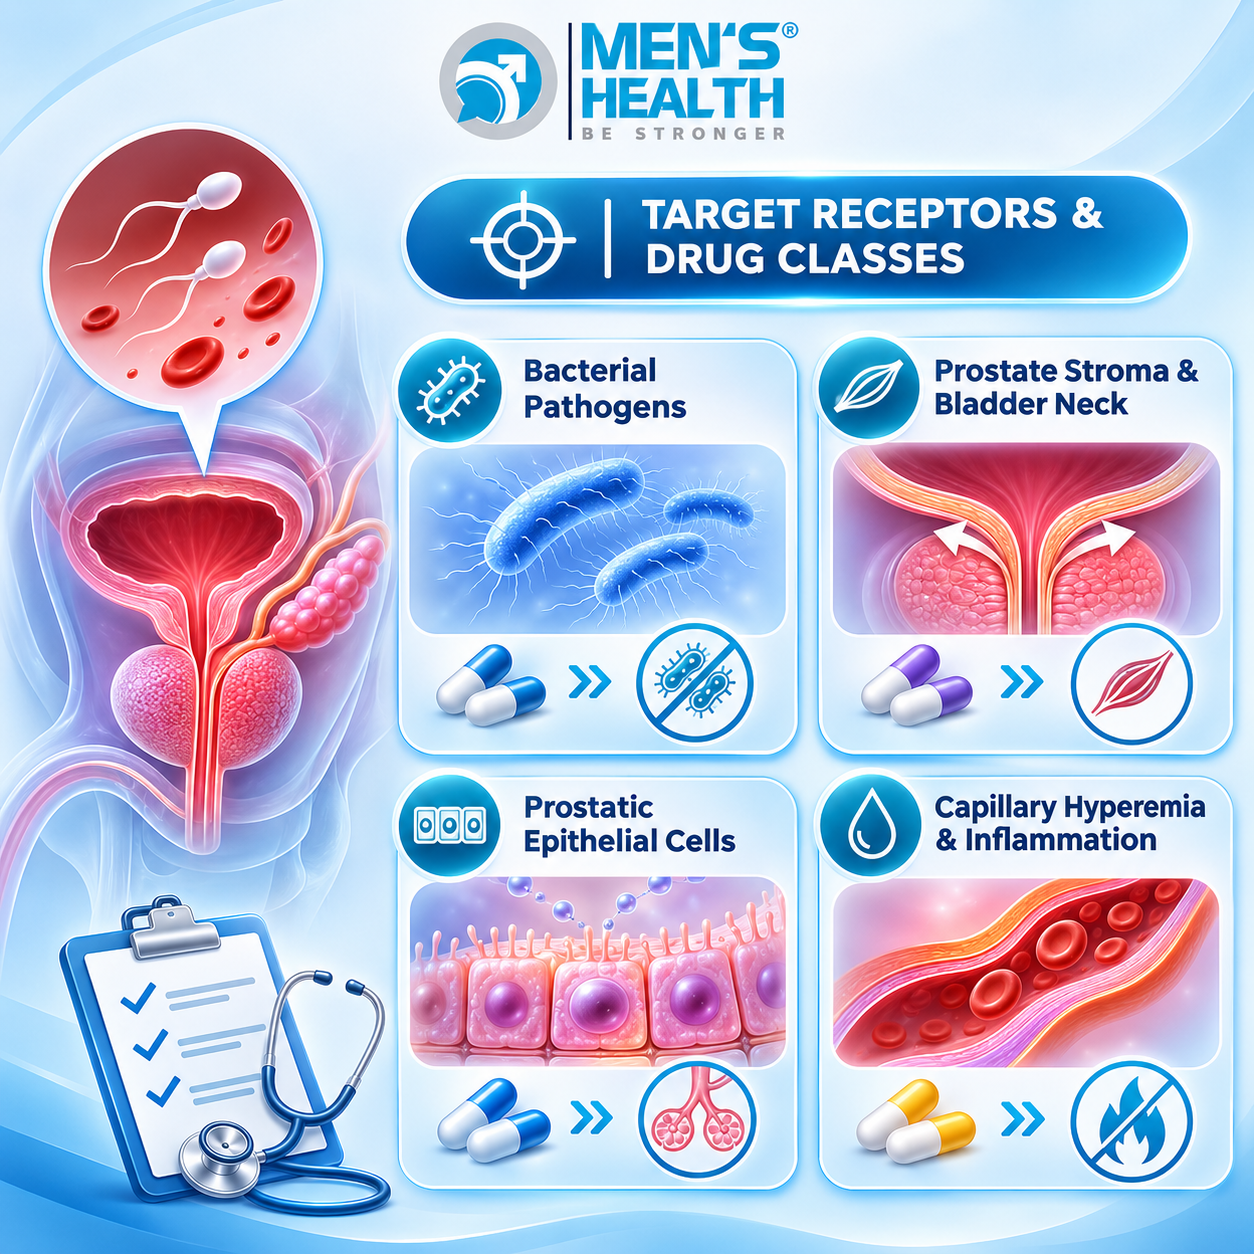
Extended-Course Lipid-Soluble Antibiotics
- Mechanism: Antimicrobial agents capable of crossing the blood-prostate barrier to achieve therapeutic concentrations within prostatic fluid and seminal vesicle tissue.
- Representative Agents: Fluoroquinolones (Ciprofloxacin, Levofloxacin), Doxycycline, Macrolides (Azithromycin).
- Indications: Recurrent hematospermia driven by chronic bacterial prostatitis or seminal vesiculitis. Extended administration (4 to 6 weeks) is frequently required.
Non-Steroidal Anti-Inflammatory Drugs (NSAIDs)
- Mechanism: Inhibits cyclooxygenase-2 (COX-2) enzymes, decreasing prostaglandin synthesis within congested pelvic tissue.
- Representative Agents: Celecoxib, Meloxicam, Ibuprofen.
- Indications: Non-bacterial inflammatory vesiculitis or chronic pelvic congestion, reducing tissue edema and capillary fragility.
Alpha-1 Adrenoceptor Antagonists (α1-Blockers)
- Mechanism: Selective blockade of α1A-adrenoceptors in the prostate stroma and bladder neck, lowering intra-prostatic voiding pressure and ejaculatory duct reflux.
- Representative Agents: Tamsulosin, Silodosin, Alfuzosin.
- Indications: Recurrent bleeding co-occurring with lower urinary tract symptoms (LUTS) or ejaculatory duct hypertension.
5-Alpha Reductase Inhibitors (5-ARIs)
- Mechanism: Inhibits conversion of testosterone to dihydrotestosterone (DHT), inducing prostatic epithelial apoptosis and suppressing subepithelial microvessel density.
- Representative Agents: Finasteride, Dutasteride.
- Indications: Refractory, persistent, or recurrent hematospermia associated with benign prostatic enlargement or friable prostatic urethral vascularity.
7. Professional Care at Men’s Health Pharmacy
Navigating recurrent male genital tract bleeding requires structured medical diagnosis, accurate risk stratification, and specialized clinical pharmacy care.
Men’s Health Pharmacy, an integral unit within the Men’s Health Center ecosystem founded by Dr. Tra Anh Duy (MD, PhD, Spec. II), provides specialized clinical pharmacy services for male reproductive and urological health. At Men’s Health, patients receive tailored consultations from experienced urologists and clinical pharmacists to ensure that prescribed therapeutic regimens—including lipid-soluble antimicrobials, anti-inflammatory agents, and α1-blockers—are calibrated precisely to diagnostic findings. The facility maintains strict clinical safety standards, individual privacy, absolute confidentiality, and evidence-based practice across all phases of patient evaluation and follow-up care.

8. Lifestyle Modifications and Long-Term Prevention
- Adequate Hydration: Maintain a daily fluid intake of 1.5 – 2.0 L to ensure regular lower tract flushing and minimize urinary concentration.
- Consistent Ejaculatory Hygiene: Maintain regular, non-strenuous ejaculatory intervals to prevent seminal vesicle stasis and fluid hyper-concentration.
- Avoidance of Perineal Trauma: Limit prolonged, unpadded bicycle riding or straddle activities that exert mechanical pressure on pelvic structures.
- Barrier Protection: Utilize condoms during non-monogamous sexual contact to prevent sexually transmitted infection acquisition and recurrence.
9. Common Clinical Pitfalls in Managing Recurrent Bleeding
- Prescribing Short-Course Antibiotics for Deep Pelvic Infection: Administering 3-to-5-day courses of standard oral antibiotics for chronic bacterial prostatitis/vesiculitis leads to incomplete bacterial eradication and early bleeding recurrence.
- Dismissing Recurrence in Patients Over 50 Years: Assuming recurrent hematospermia in older males is benign without ordering serum PSA testing or pelvic mpMRI to exclude prostate adenocarcinoma.
- Confusing Hematospermia with Gross Hematuria: Failing to verify whether blood appears exclusively in ejaculate or throughout voided urine leads to misdirected diagnostic testing.
- Unsupervised Self-Medication: Self-administering unprescribed antibiotics or herbal supplements risks delaying the diagnosis of structural or neoplastic conditions.
10. Recurrent Hematospermia: Frequently Asked Questions
Can hematospermia recur after successful initial treatment?
Yes. Hematospermia can recur if the primary cause – such as a deep prostatic bacterial infection, intra-prostatic cyst, calcification, or friable urethral vascularity – was incompletely resolved or if new tissue inflammation develops.
Does recurrent blood in semen always indicate prostate cancer?
No. The majority of recurrent hematospermia cases stem from benign etiologies such as chronic vesiculitis, prostatic calculi, or vascular micro-trauma. However, in men over 50 years of age, recurrence warrants thorough diagnostic evaluation (including PSA and pelvic mpMRI) to exclude prostate adenocarcinoma.
How long does it take for oxidized blood to clear from the seminal vesicles?
Dark brown or rusty ejaculate reflects old blood stored within the seminal vesicles. It typically requires multiple voiding and ejaculatory cycles (often taking 2 to 6 weeks) to clear completely following the resolution of active bleeding.
When is advanced pelvic mpMRI necessary for recurrent hematospermia?
Pelvic mpMRI is indicated when hematospermia is recurrent (lasting >4-8 weeks), fails initial conservative/antimicrobial therapy, is accompanied by red flag symptoms, or occurs in males aged >50 years with elevated serum PSA levels.
Should sexual activity be paused during recurrent hematospermia?
A brief period of sexual rest (a few days) can be helpful during acute inflammatory flares. However, once acute infection is addressed under medical supervision, regular, non-strenuous ejaculation aids in clearing residual fluid stasis.
Conclusion and Expert Clinical Advice
Recurrent hematospermia and male genital tract bleeding warrant systematic clinical re-evaluation to differentiate persistent benign inflammation from structural ductal anomalies, vascular malformations, or prostate malignancy. Utilizing high-resolution imaging (pelvic mpMRI), serum PSA testing, and targeted endourological investigations allows clinicians to identify the exact cause and guide management safely.
Patients experiencing recurrent blood in their ejaculatory fluid should avoid self-diagnosis and refrain from taking unprescribed medications. Seeking direct clinical evaluation at a specialized urological facility such as the Men’s Health Center guarantees precise diagnostic assessment, specialist physician management, and dedicated clinical pharmacy support for long-term urological and reproductive health.